Volume & Issue: Volume 2, Issue 6, November and December 2026 
Number of Articles: 8

Effect of Intraoperative Dexmedetomidine Administration on Postoperative Delirium Scores During the First 72 Hours: A Randomized Controlled Trial

Pages 518-526

https://doi.org/10.5281/zenodo.22059659

Sima Miraghaei, Mansour Rezaei

Abstract Introduction: Postoperative delirium is a frequent complication associated with prolonged recovery, increased morbidity, and higher healthcare costs. Dexmedetomidine may reduce delirium through its sedative, analgesic-sparing, and sympatholytic effects, although evidence remains inconsistent. This randomized controlled trial aimed to evaluate the effect of intraoperative dexmedetomidine administration on postoperative delirium scores during the first 72 hours.

Material and methods: In this double-blind, randomized controlled trial conducted at Imam Reza Hospital, 50 surgical patients were allocated (1:1) to receive either intraoperative dexmedetomidine (0.5 µg/kg bolus, then 0.2–0.5 µg/kg/h infusion) or 0.9% normal saline. Postoperative delirium was evaluated during the first 72 hours using the Confusion Assessment Method (CAM/CAM-S).

Results: Across the first 72 postoperative hours, the dexmedetomidine group showed consistently lower delirium severity and incidence than controls, with the greatest separation at 24–48 hours; delirium scores peaked early and then declined in both groups, but remained lower with dexmedetomidine at every assessment (all time points: P<0.05). In parallel, the dexmedetomidine group had lower intraoperative heart rate and slightly lower mean arterial pressure, along with significantly lower postoperative VAS pain scores from 1 to 24 hours (all comparisons: P<0.05).

Conclusion: Intraoperative dexmedetomidine appears to reduce early postoperative delirium burden while improving analgesia and maintaining acceptable hemodynamic stability. These findings support its role as a useful perioperative adjunct, likely through attenuation of surgical stress, sympathetic activation, and pain-related neurocognitive disruption.

Preoperative Sarcopenia in Esophagectomy: Effects on Short-Term Surgical Complications, Anastomotic Leakage, and Hospital Stay

Pages 527-536

https://doi.org/10.5281/zenodo.22059783

Amin Kamyab, Hosein Shiri

Abstract Introduction: Esophagectomy is a high-risk operation often complicated by postoperative morbidity, especially anastomotic leakage, pulmonary complications, and prolonged hospitalization. Because sarcopenia reflects reduced physiologic reserve and impaired recovery potential, it may help identify patients at greater risk for poor short-term outcomes. Therefore, this study aimed to evaluate the impact of preoperative sarcopenia on short-term surgical complications, anastomotic leakage, and hospital stay.

Material and methods: This descriptive cross-sectional study included 75 adults undergoing elective esophagectomy at Imam Reza Hospital, Tabriz. Participants were recruited by convenience sampling. Preoperative sarcopenia was assessed using L3-level computed tomography to calculate the skeletal muscle index, and its associations with postoperative complications, anastomotic leakage, intensive care and hospital stay were evaluated using clinical and surgical data.

Results: Preoperative sarcopenia was associated with higher rates of overall complications, pulmonary complications, anastomotic leakage, surgical-site infection, atrial fibrillation, and 30-day readmission/mortality, as well as longer hospital and ICU stays. In adjusted analyses, sarcopenia remained an independent predictor of adverse outcomes, including overall complications (AOR 2.10, 95% CI 1.20–3.68; P=0.009), anastomotic leakage (AOR 2.35, 95% CI 1.01–5.47; P=0.047), pulmonary complications (AOR 2.80, 95% CI 1.40–5.60; P=0.003), major morbidity (AOR 2.65, 95% CI 1.30–5.40; P=0.007), and prolonged hospital stay (AOR 1.95, 95% CI 1.10–3.45; P=0.021).

Conclusion: Preoperative sarcopenia appears to be a clinically meaningful marker of poor short-term recovery after esophagectomy. Its association with increased postoperative complications and prolonged hospitalization supports routine preoperative muscle assessment to improve risk stratification and guide targeted perioperative optimization.

Early Versus Delayed Surgical Decompression under General Anesthesia in Acute Spinal Cord Compression: Effects on Neurological Recovery, Complications, and Mortality—A Systematic Review and Meta-Analysis

Pages 537-550

https://doi.org/10.5281/zenodo.22286215

Ali Mohamadi Moghadam, Rana Mohammad Yousef, Robab Azizi, Roxana Hessam, Maryam Milanifard

Abstract Background: Acute spinal cord compression following traumatic spinal cord injury (SCI) represents a neurosurgical emergency with profound implications for patient outcomes. The optimal timing of surgical decompression remains a subject of considerable debate despite growing evidence supporting early intervention. This systematic review and meta-analysis evaluates the comparative effectiveness of early (≤24 hours) versus delayed (>24 hours) surgical decompression performed under general anesthesia on neurological recovery, complication rates, and mortality in patients with acute spinal cord compression.

Methods: A comprehensive literature search conducted across PubMed, Embase, Cochrane Central Register of Controlled Trials, Web of Science, and Scopus from database inception through April 2024. Studies comparing early versus delayed surgical decompression in adult patients with acute traumatic spinal cord compression were included. The primary outcome was neurological improvement measured by changes in American Spinal Injury Association (ASIA) Impairment Scale (AIS) grade and ASIA Motor Score (AMS). Secondary outcomes included postoperative complications and all-cause mortality.

Results: Fourteen studies comprising 2,505 patients met inclusion criteria. Early surgical decompression demonstrated a non-significant trend toward improved neurological recovery (MD 3.64 points in AMS; 95% CI: -0.05 to 7.33; p=0.05) and a 37% higher odds of achieving at least one-grade AIS improvement (OR 1.37; 95% CI: 0.90-2.10; p=0.14). Early surgery significantly reduced postoperative complications (RR 0.42; 95% CI: 0.20-0.88; p=0.02) and shortened hospital length of stay. Mortality rates were comparable between groups (OR 1.27; 95% CI: 0.30-5.38; p=0.75). Subgroup analyses revealed greater benefits in patients with complete SCIs.

Conclusion: Early surgical decompression within 24 hours of injury appears safe and may confer neurological benefits, with significant reductions in complications and hospital stay. These findings support institutional protocols prioritizing expedited surgical intervention when clinically feasible.

Anesthetic and Perioperative Predictors of Neurological Deterioration and Mortality Following Emergency Craniotomy for Acute Brain Injury: A Systematic Review and Meta-Analysis

Pages 551-564

https://doi.org/10.5281/zenodo.22286357

Ali Mohamadi Moghadam, Rana Mohammad Yousef, Robab Azizi, Roxana Hessam, Maryam Milanifard

Abstract Background: Emergency craniotomy is a life-saving intervention for patients with acute brain injury (ABI), yet it carries a significant risk of postoperative neurological deterioration and mortality. Identifying modifiable anesthetic and perioperative predictors is crucial for improving outcomes. This systematic review and meta-analysis aims to quantify the association between specific perioperative factors and adverse outcomes following emergency craniotomy for ABI.

Methods: A systematic search of PubMed, Embase, and the Cochrane Library conducted from inception to January 2026. We included observational studies and randomized controlled trials reporting on adult patients undergoing emergency craniotomy for traumatic brain injury (TBI), intracerebral hemorrhage (ICH), or subarachnoid hemorrhage (SAH). Studies were required to report data on anesthetic or perioperative predictors and their association with neurological deterioration or mortality. Pooled odds ratios (ORs) were calculated using random-effects models.

Results: Twenty-five studies comprising 4,872 patients were included. The overall 30-day mortality rate was 28.5%. Significant perioperative predictors of mortality included intraoperative hypotension (systolic blood pressure <90 mmHg; OR=2.45, 95% CI: 1.78-3.36, p<0.001), prolonged operative time (>4 hours; OR=1.89, 95% CI: 1.45-2.47, p<0.001), and high intraoperative blood transfusion volume (>4 units; OR=2.11, 95% CI: 1.55-2.87, p<0.001). Predictors of neurological deterioration included postoperative hyperglycemia (>180 mg/dL; OR=2.98, 95% CI: 2.01-4.42, p<0.001) and early postoperative seizures (OR=3.45, 95% CI: 2.12-5.61, p<0.001). The use of total intravenous anesthesia (TIVA) was associated with a non-significant trend towards reduced neurological deterioration (OR=0.78, 95% CI: 0.59-1.03, p=0.08).

Conclusion: This meta-analysis identifies key modifiable perioperative factors—hypotension, prolonged surgery, and blood transfusion—as significant predictors of mortality. Strict glycemic control and seizure prophylaxis are critical to preventing neurological decline. These findings underscore the need for targeted perioperative protocols to mitigate these risks and improve outcomes in this high-risk patient population.

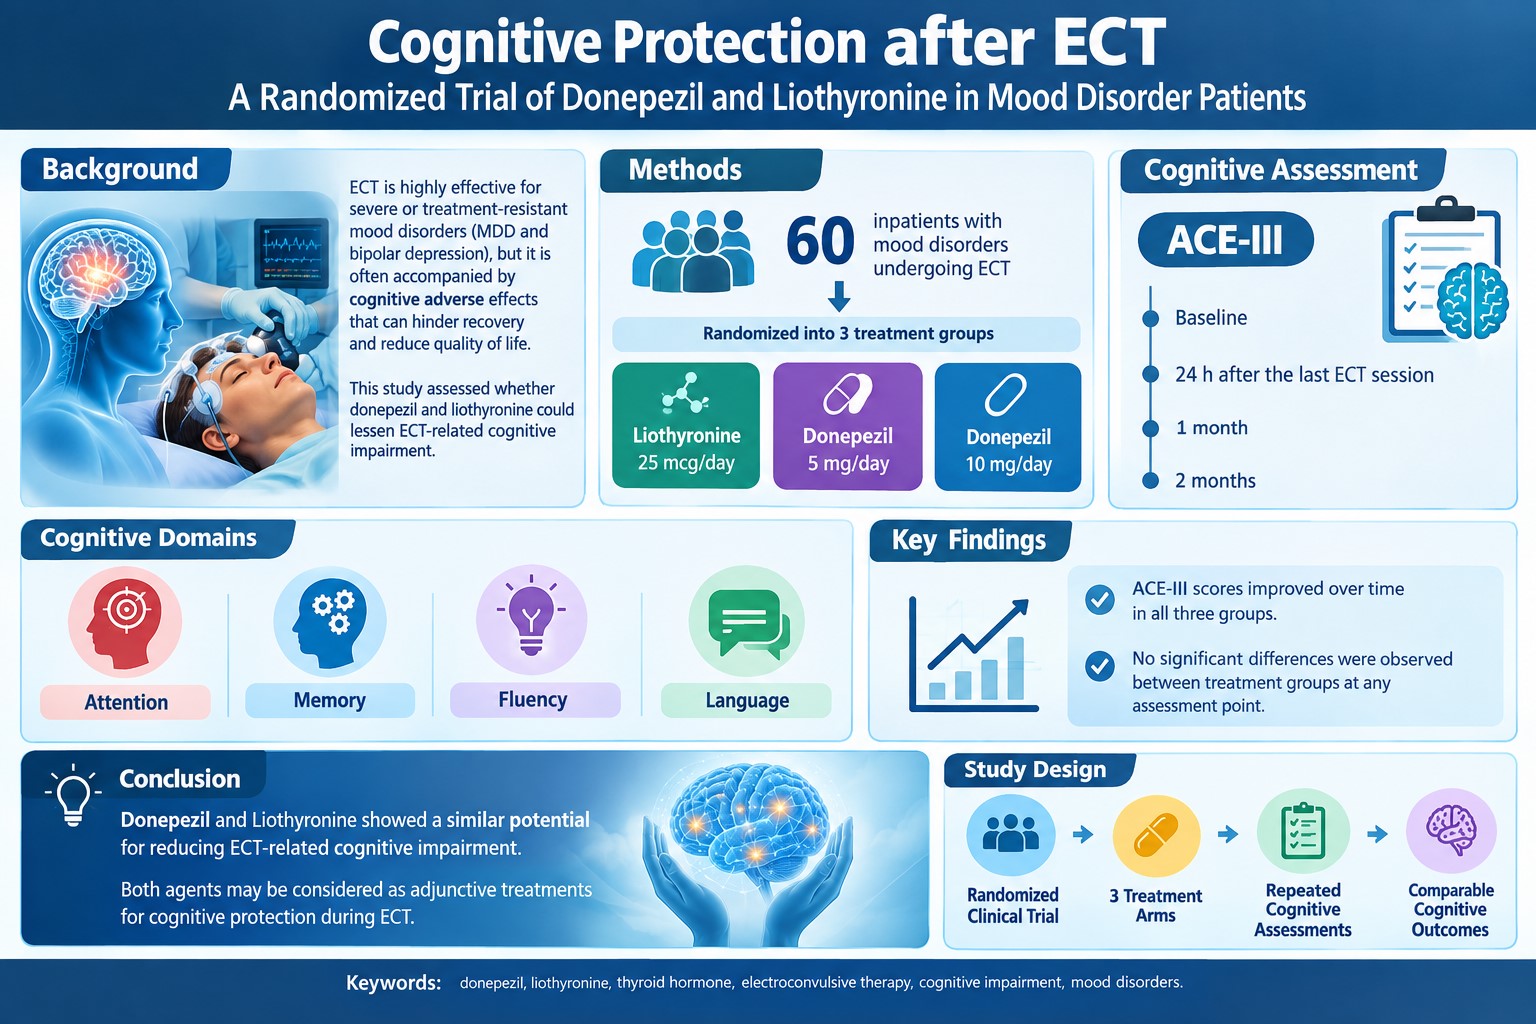
Cognitive Protection after ECT: A Randomized Trial of Donepezil and Liothyronine in Mood Disorder Patients

Pages 565-569

https://doi.org/10.5281/zenodo.22689203

Angela Hamidia, Hamid Sadegh, Mahfam Mojazi-Amiri

Abstract Background: Electroconvulsive therapy (ECT) is one of the most effective interventions available for severe or treatment-resistant mood disorders such as major depressive disorder (MDD) and bipolar depression, yet it is commonly accompanied by cognitive adverse effects that can hinder recovery and reduce quality of life. This trial was designed to assess whether donepezil, a cholinesterase inhibitor, and liothyronine, a synthetic thyroid hormone, could lessen the cognitive impairment that often follows ECT.

Methods: Sixty inpatients with mood disorders scheduled for ECT were allocated at random to one of three arms — liothyronine 25 mcg/day, donepezil 5 mg/day, or donepezil 10 mg/day. Cognition was evaluated with the Addenbrooke’s Cognitive Examination, Third Edition (ACE-III), before treatment began, 24 hours after the last ECT session, and again at one and two months afterward.

Results: Scores on the ACE-III rose over time in every arm across the attention, memory, fluency, and language domains, and none of the three groups differed significantly from one another at any assessment point — indicating that donepezil and liothyronine conferred a similar degree of cognitive protection.

Conclusion: Both donepezil and liothyronine appear effective in reducing ECT-related cognitive impairment. Either agent may reasonably be considered as an adjunctive treatment to help preserve cognitive function in patients undergoing ECT.

Comparison of Preoperative Serum Albumin and C-Reactive Protein Levels in Relation to Surgical Site Infection Following Femoral Implant Placemen

Pages 570-581

https://doi.org/10.5281/zenodo.22735718

Parham Maroufi, Alireza Aghili

Abstract Introduction: Surgical site infections following femoral implant placement cause severe morbidity, often driven by host malnutrition and baseline inflammation. Serum albumin and C-reactive protein (CRP) reflect metabolic reserve and systemic inflammatory tone, respectively. Therefore, this study aimed to compare preoperative serum albumin and CRP levels in relation to surgical site infection incidence following femoral implant placement.

Material and methods: This analytical cross-sectional study enrolled 125 consecutive patients undergoing primary femoral implant surgery at shohada Hospital, Tabriz. Baseline preoperative serum albumin and C-reactive protein concentrations were quantified alongside comprehensive clinical and operative variables. Patients underwent systematic surveillance over a 90-day postoperative period to adjudicate surgical site infections based on CDC/NHSN criteria, evaluating biomarker predictive performance through comparative and multivariable regression analyses.

Results: Patients developing surgical site infections demonstrated significantly reduced preoperative serum albumin (3.12±0.46 versus 3.89±0.49 g/dL; P<0.001) and elevated hs-CRP concentrations (20.38±6.84 versus 7.31±4.58 mg/L; P<0.001). Multivariable logistic regression identified preoperative hypoalbuminemia (aOR=7.845, 95% CI: 1.614 to 38.128; P=0.011), elevated hs-CRP (aOR=9.132, 95% CI:1.684 to 49.524; P=0.010), low albumin-to-CRP ratio (aOR=11.418, 95% CI: 1.925 to 67.726; P=0.007), and prolonged operative duration (aOR=4.892; P=0.044) as independent infection predictors.

Conclusion: Preoperative hypoalbuminemia and elevated C-reactive protein levels are potent independent predictors of postoperative surgical site infections following femoral hardware fixation. Preoperative screening with these cost-effective biomarkers, particularly the composite albumin-to-CRP ratio, facilitates early risk stratification and enables targeted nutritional and anti-inflammatory interventions to mitigate implant infection rates.

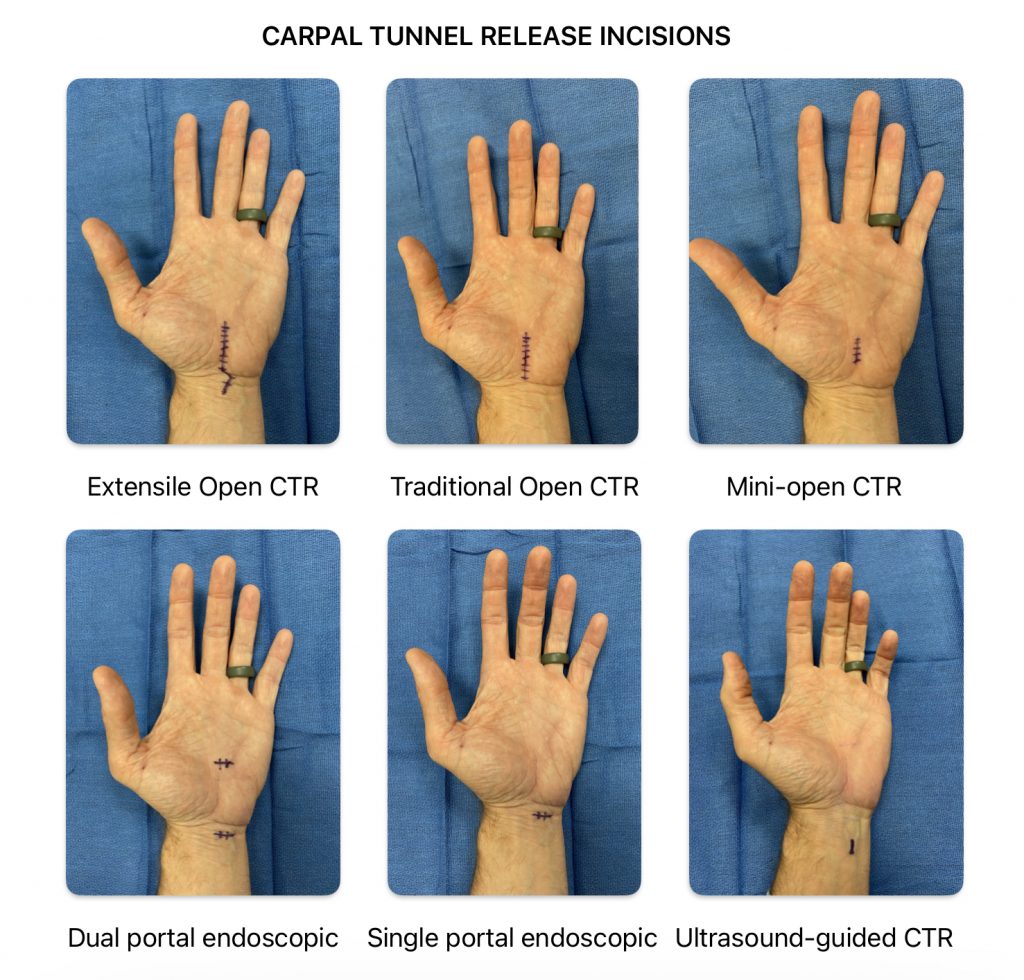
Assessment of the Incidence and Predictors of Revision Surgery Following Carpal Tunnel Release

Pages 582-592

https://doi.org/10.5281/zenodo.22735845

Mohammad Reza Moharrami, Alireza Aghili

Abstract Introduction: Carpal tunnel release is highly effective; however, a subset of patients develops persistent or recurrent symptoms requiring revision surgery. Failure may reflect incomplete decompression, perineural scarring, technical injury, or patient-related systemic and occupational factors. This study aimed to assess the incidence of revision surgery and identify its independent predictors following primary carpal tunnel release.

Material and methods: This retrospective, descriptive cross-sectional study was conducted at Imam Reza Hospital, Tabriz, Iran, and included 300 adults who underwent primary carpal tunnel release. Eligible records were selected through convenience sampling. Demographic, clinical, electrophysiological, surgical, postoperative, and revision-related data were extracted from medical records using a standardized form and analyzed statistically to determine the incidence and predictors of revision surgery.

Results: Revision carpal tunnel surgery occurred in 8.0% of patients. Multivariable logistic regression identified preoperative severe electrodiagnostic grade (adjusted OR=3.86, 95% CI:1.31–11.38; P=0.014), persistent postoperative pillar or scar pain (adjusted OR=3.41, 95% CI:1.18–9.85; P=0.023), primary endoscopic release (adjusted OR=3.25, 95% CI:1.04–10.15; P=0.043), preoperative thenar atrophy (adjusted OR=3.12, 95% CI:1.08–8.99; P=0.035), and diabetes mellitus (adjusted OR=2.94, 95% CI:1.05–8.24; P=0.040) as independent predictors of revision surgery.

Conclusion: Secondary revision following carpal tunnel release is primarily driven by advanced baseline neural degeneration, metabolic comorbidity, endoscopic decompression, and persistent postoperative pillar pain. Comprehensive preoperative electrodiagnostic risk stratification, careful surgical technique selection, and targeted glycemic management are essential to mitigate surgical failure rates and optimize long-term clinical recovery.

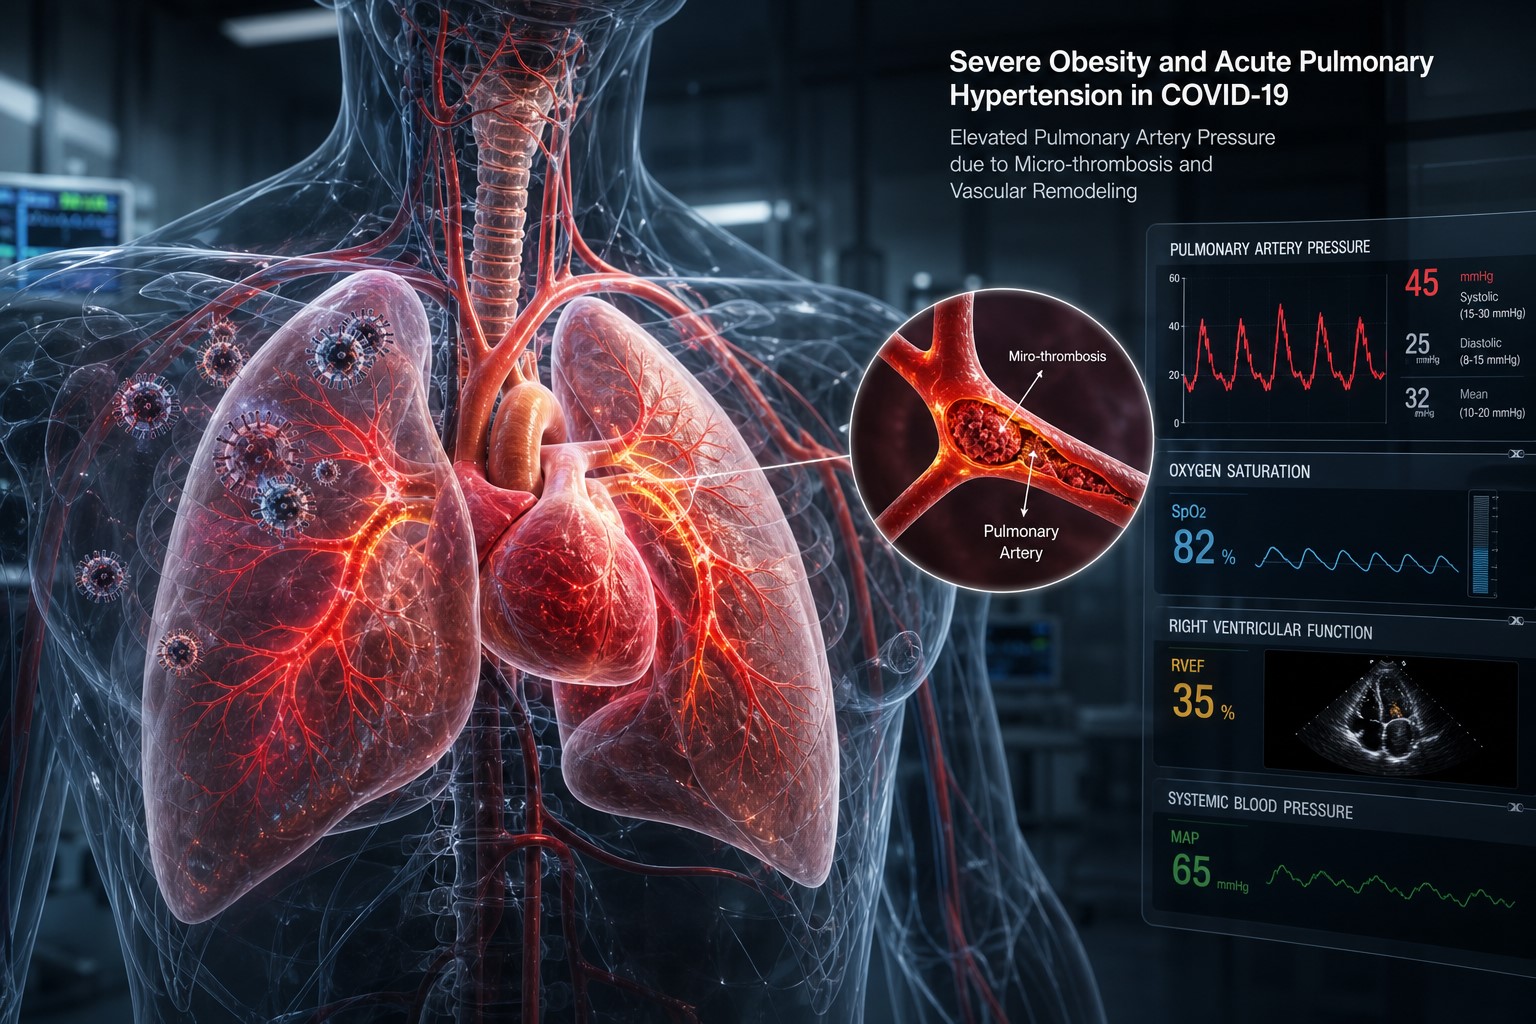
Incidence of Pulmonary Hypertension in Obese Patients with COVID-19 in Intensive Care Units

Pages 593-599

https://doi.org/10.5281/zenodo.22735930

Mir Mohammad Taghi Mortazavi, Mansour Rezaei, Mozhdeh Nikfar

Abstract Introduction: COVID-19 often triggers acute pulmonary hypertension, a life-threatening vascular complication whose risk is markedly amplified by obesity in critically ill patients. However, the precise incidence of this hemodynamic condition within intensive care settings remains inadequately quantified. Therefore, this study aimed to determine the incidence of pulmonary hypertension in obese COVID-19 patients admitted to intensive care units.

Material and methods: This descriptive cross-sectional study was conducted at Imam Reza Hospital. Using convenience sampling and the Cochran formula, a sample of 71 obese COVID-19 patients was recruited. The procedure involved comprehensive assessment of hemodynamic parameters, including pulmonary artery pressures, oxygen saturation, and anthropometric data, to evaluate the incidence of pulmonary hypertension in the intensive care setting.

Results: In critically ill COVID-19 patients, pulmonary hypertension (PH) was associated with higher BMI (36.5±3.4 vs. 32.8±2.9 kg/m²; p=0.002), elevated APACHE II scores (18.6±4.1 vs. 14.8±3.5; p=0.001), longer ICU stay (14.1±5.6 vs. 11.2±4.2 days; p=0.015), and severe impairment in PASP (48.6±7.5 mmHg; p<0.001), mPAP (32.4±5.6 mmHg; p<0.001), PaO2/FiO2 (165.2±38.6; p=0.004), D-dimer (2800 ng/mL; p=0.001), and CRP (72.8±18.5 mg/L; p=0.003). Class III obesity independently portended the greatest risk (OR=7.95; p<0.001).

Conclusion: Severe obesity independently drives acute pulmonary vascular complications in critically ill COVID-19 patients, significantly worsening hemodynamics, oxygenation, systemic inflammation, and clinical outcomes. Escalating adiposity classes exhibit a clear dose-dependent risk of pulmonary hypertension. Early hemodynamic evaluation and targeted vascular therapies are imperative in obese ICU patients with COVID-19 to mitigate microvascular injury and improve survival.