Volume & Issue: Volume 3, Issue 1, January and February 2027 
Number of Articles: 15

Telemedicine Integration in Emergency Care: Effects on Clinical Outcomes, Workflow Efficiency, and Patient Satisfaction—A Systematic Review

Pages 1-16

https://doi.org/10.22034/jampbr.2026.596936.1112

Roxana Hessam, Maryam Milanifard

Abstract Background: Emergency care systems worldwide face increasing challenges due to overcrowding, limited specialist availability, geographic disparities, and the need for rapid clinical decision-making. Telemedicine has emerged as an innovative approach to improve access to expert consultation, optimize emergency department (ED) workflows, and enhance patient-centered care. This systematic review evaluates the effects of telemedicine integration in emergency care on clinical outcomes, workflow efficiency, and patient satisfaction.

Methods: A systematic review conducted following the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines. Electronic databases including PubMed, Embase, Scopus, Web of Science, and Cochrane Library searched for studies evaluating telemedicine applications in emergency care. Eligible studies included randomized controlled trials, prospective and retrospective observational studies, and comparative studies reporting clinical outcomes, operational performance, or patient satisfaction measures. Data regarding study characteristics, telemedicine models, emergency conditions, outcomes, and quality indicators extracted and synthesized.

Results: 28 studies involving more than 120,000 emergency care encounters were included. Telemedicine implementation was associated with improved access to specialist consultation, reduced time-to-treatment, decreased emergency department length of stay, and enhanced diagnostic decision-making. The greatest benefits observed in stroke, trauma, cardiac emergencies, and rural emergency care settings. Meta-analysis demonstrated a significant reduction in treatment delays and improved workflow efficiency. Patient satisfaction was generally high, with users reporting improved communication, reduced travel burden, and increased confidence in medical decisions. However, challenges included technological limitations, provider training requirements, and integration with existing healthcare systems.

Conclusion: Telemedicine represents an effective strategy for improving emergency care delivery by enhancing clinical decision-making, accelerating treatment processes, and improving patient experiences. Successful implementation requires reliable technological infrastructure, standardized clinical protocols, and continuous evaluation of outcomes. Future research should focus on large-scale randomized studies and cost-effectiveness analyses to optimize telemedicine integration into emergency healthcare systems.

Dynamic Causal Modeling of Heart Rate–Blood Pressure Coupling During Induction of Anesthesia: A Systems-Based Approach to Predict Vasopressor Requirements

Pages 17-28

https://doi.org/10.5281/zenodo.21969633

Robab Azizi, Rana Mohammad Yousef

Abstract Background: Induction of general anesthesia frequently induces hemodynamic instability characterized by hypotension, necessitating timely administration of vasopressors. The causal relationship between heart rate (HR) and blood pressure (BP) during this critical period remains incompletely understood, limiting the development of predictive models for vasopressor requirements.

Objective: This study employed dynamic causal modeling (DCM) to characterize the directional interactions between HR and BP during anesthetic induction and to develop a systems-based predictive framework for vasopressor needs.

Methods: We prospectively enrolled 120 adult patients undergoing elective major surgery under general anesthesia. Continuous HR and invasive arterial BP data were recorded from 5 minutes pre-induction to 10 minutes post-intubation. A time-varying Granger causality analysis was applied to quantify the feedforward (HR→BP) and feedback (BP→HR) causal pathways. A dynamic Bayesian network integrating hemodynamic, pharmacodynamic, and patient-specific parameters was constructed to predict vasopressor requirements.

Results: Propofol induction significantly attenuated the feedback pathway (BP→HR) from baseline (causal coefficient: 0.42±0.11 vs. 0.18±0.09, p<0.001) while preserving the feedforward pathway (HR→BP). The magnitude of feedback attenuation correlated strongly with subsequent vasopressor dose (r=0.73, p<0.001). The DCM-based prediction model achieved an AUC of 0.89 (95% CI: 0.83-0.94) for predicting vasopressor requirements >50 µg phenylephrine equivalent.

Conclusion: Dynamic causal modeling of HR-BP coupling during anesthetic induction provides mechanistic insights into hemodynamic instability and enables accurate, individualized prediction of vasopressor requirements, offering a promising framework for precision hemodynamic management.

Emergency Department-Based Frailty Assessment Tools for Predicting Hospitalization, Mortality, and Adverse Outcomes in Older Adults: A Systematic Review and Meta-analysis

Pages 29-41

https://doi.org/10.5281/zenodo.21969661

Roxana Hessam, Maryam Milanifard

Abstract The increasing proportion of older adults presenting to emergency departments (EDs) has created significant challenges for healthcare systems worldwide. Older patients frequently present with complex multimorbidity, functional impairment, cognitive decline, and increased vulnerability to acute stressors. Frailty, defined as a state of decreased physiological reserve and increased susceptibility to adverse health outcomes, has emerged as an important predictor of hospitalization, mortality, and functional deterioration. Emergency department-based frailty assessment tools may provide rapid identification of high-risk older adults and support individualized clinical decision-making. This systematic review and meta-analysis aimed to evaluate the predictive performance of frailty assessment instruments applied in emergency departments for hospitalization, mortality, and other adverse outcomes among older adults. A comprehensive literature search performed in major biomedical databases to identify studies evaluating validated frailty assessment tools in ED populations aged ≥65 years. Eligible studies assessed the association between frailty measurements and clinical outcomes, including hospital admission, short- and long-term mortality, intensive care utilization, functional decline, and adverse events. Data regarding study characteristics, frailty instruments, predictive performance measures, and outcomes extracted and synthesized. The pooled evidence demonstrated that ED-based frailty assessment tools were significantly associated with increased risk of hospitalization and mortality. Instruments including the Clinical Frailty Scale (CFS), Identification of Seniors at Risk (ISAR), Emergency Department Frailty Index (ED-FI), and Frailty Phenotype demonstrated moderate-to-high predictive accuracy. Frailty assessment improved risk stratification beyond chronological age alone and provided clinically meaningful information regarding patient vulnerability. However, heterogeneity existed regarding assessment methods, outcome definitions, and follow-up periods. Frailty screening in emergency departments represents a valuable approach for identifying older adults at increased risk of adverse outcomes. Integration of rapid frailty assessment into routine emergency care may improve triage decisions, facilitate appropriate resource allocation, and support patient-centered management strategies.

Incidence of Pulmonary Vascular Thrombosis in Intensive Care Units Following COVID-19 Vaccination

Pages 42-50

https://doi.org/10.5281/zenodo.22736966

Mir Mohammad Taghi Mortazavi, Mehdi khanbabayi Gol, Mozhdeh Nikfar

Abstract Introduction: While COVID-19 vaccines substantially reduced global mortality, rare hypercoagulable safety signals such as immunothrombosis emerged. In critically ill ICU patients, pre-existing systemic inflammation and endothelial strain may compound these thrombotic risks within the delicate pulmonary vasculature. Consequently, this study aimed to evaluate the incidence and clinical characteristics of pulmonary vascular thrombosis in ICU patients following COVID-19 vaccination.

Material and methods: This cross-sectional study was conducted at Imam Reza Center, Tabriz, recruiting 250 ICU patients selected via convenience sampling based on Cochran’s formula. Eligible post-vaccination patients were evaluated for pulmonary vascular thrombosis using CTPA. Demographic, clinical, hemodynamic, and laboratory data—including D-dimer and anti-PF4 levels—were abstracted from medical records and analyzed to identify clinical predictors.

Results: Pulmonary vascular thrombosis significantly correlated with thrombocytopenia (61.8% vs. 17.6%, P < 0.001), elevated D-dimer (6.84±3.42 vs. 2.22±1.28 mg/L FEU, P<0.001), and higher mPAP (31.40±8.24 vs. 22.33±4.98 mmHg, P<0.001). Multivariable regression identified anti-PF4 positivity (aOR:6.842, 95% CI:2.418–19.362, P<0.001), thrombocytopenia (aOR:3.428, 95% CI:1.584–7.418, P=0.002), and adenoviral vaccination (aOR:2.815, 95% CI:1.382–5.735, P=0.004) as independent predictors.

Conclusion: Post-vaccination pulmonary vascular thrombosis in critically ill patients is independently driven by adenoviral vector platforms, thrombocytopenia, and anti-PF4 seropositivity, leading to marked hemodynamic compromise. Routine screening with D-dimer, platelet counts, and anti-PF4 antibody assays facilitates early risk stratification, timely intervention, and mitigated ICU mortality.

The Role of Magnetic Resonance Imaging in the Evaluation of Synovitis and Occult Infection Following Total Knee Arthroplasty: A Systematic review

Pages 51-56

https://doi.org/10.5281/zenodo.22737059

Hamed Ghafari, Mahnaz Ranjkesh

Abstract Introduction: Magnetic resonance imaging has emerged as a valuable adjunctive tool for evaluating persistent symptoms following total knee arthroplasty, particularly in differentiating synovitis from occult periprosthetic infection. Advances in metal artifact reduction techniques have expanded MRI’s diagnostic utility, enabling improved visualization of periprosthetic soft tissues and inflammatory changes that are often inadequately assessed by conventional diagnostic methods.

Material and methods: This systematic review comprehensively searched major databases without time limits to evaluate the effectiveness of MRI in detecting synovitis and occult infection after total knee arthroplasty.

Results: Magnetic resonance imaging provides a comprehensive assessment of symptomatic patients after total knee arthroplasty by capturing both prevalent inflammatory changes and diagnostically specific features. While synovitis is common and often reflects aseptic pathology, findings such as bone marrow edema, periprosthetic fluid collections, and sinus tracts enhance diagnostic discrimination, supporting MRI as a valuable adjunct for identifying or excluding occult periprosthetic joint infection.

Conclusion: The relatively high negative predictive value of MRI has significant clinical implications, particularly in excluding infection in symptomatic patients. A negative MRI study, characterized by the absence of marrow edema, significant fluid collections, or aggressive soft tissue abnormalities, provides reassurance that infection is unlikely.

Comparison of Internal Fixation Outcomes in Basicervical Femoral Neck Fractures Using Dynamic Hip Screw Combined with Partial Threaded vs. Fully Threaded Anti-Rotational Screws: Randomized clinical Trial

Pages 57-64

https://doi.org/10.5281/zenodo.22815685

Alireza Sadeghpour Teymourlou, Saeed Nouri

Abstract Introduction: Basicervical femoral neck fractures are unstable injuries often resulting from trauma, particularly in patients with multitrauma. Effective fixation must ensure mechanical stability and allow early mobilization. This study compares the outcomes of dynamic hip screw (DHS) fixation combined with either a partially or fully threaded anti-rotational screw in traumatic basicervical fractures, aiming to identify the more effective method for improving clinical results in this challenging patient population.

Material and methods: This randomized, double-blind clinical trial was conducted at Shahda Hospital, affiliated with Tabriz University of Medical Sciences(2024-2025), involving approximately 50 patients with basicervical femoral neck fractures. Patients were randomly assigned to two groups: Group A underwent fixation with a Dynamic Hip Screw (DHS) plus a partially threaded anti-rotational screw, while Group B received DHS with a fully threaded anti-rotational screw.

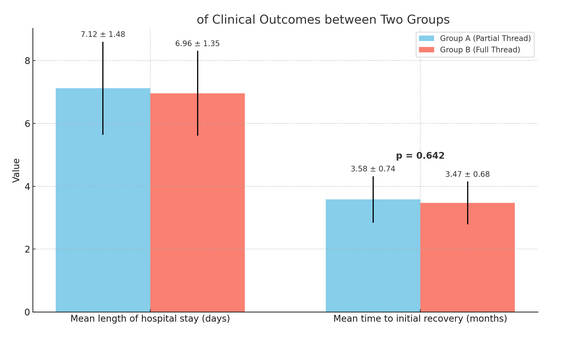
Results: There were no significant differences between Group A and Group B in hospital stay (p=0.620), time to recovery (p=0.642), chronic pain incidence (p=0.545), avascular necrosis (p=0.402), non-union and infection rates (both p=0.321), or surgical success (p=0.572). Additionally, Harris Hip Score components and hip function measures at follow-ups showed no significant differences, with all p-values above 0.27, indicating comparable outcomes between the two fixation methods.

Conclusion: Based on the findings of this study, there were no statistically significant differences between partial thread and full thread screw fixation in treating basicervical femoral neck fractures regarding functional hip outcomes, postoperative complications, Harris Hip Scores, or early recovery parameters.

Efficacy of Proximal Femoral Nail Antirotation (PFNA) in Managing Proximal Femoral Fractures: A Systematic Review of Short- and Long-Term Outcomes

Pages 65-73

https://doi.org/10.5281/zenodo.22816007

Saeed Nouri

Abstract Introduction: Proximal femoral fractures present significant biomechanical fixation challenges, particularly within osteoporotic bone. Although the Proximal Femoral Nail Antirotation (PFNA) provides theoretical rotational and load-sharing advantages via helical blade compaction, clinical evidence regarding sustained performance remains inconsistent. Therefore, this systematic review comprehensively evaluated the short- and long-term clinical, radiological, and functional outcomes of PFNA in proximal femoral fractures.

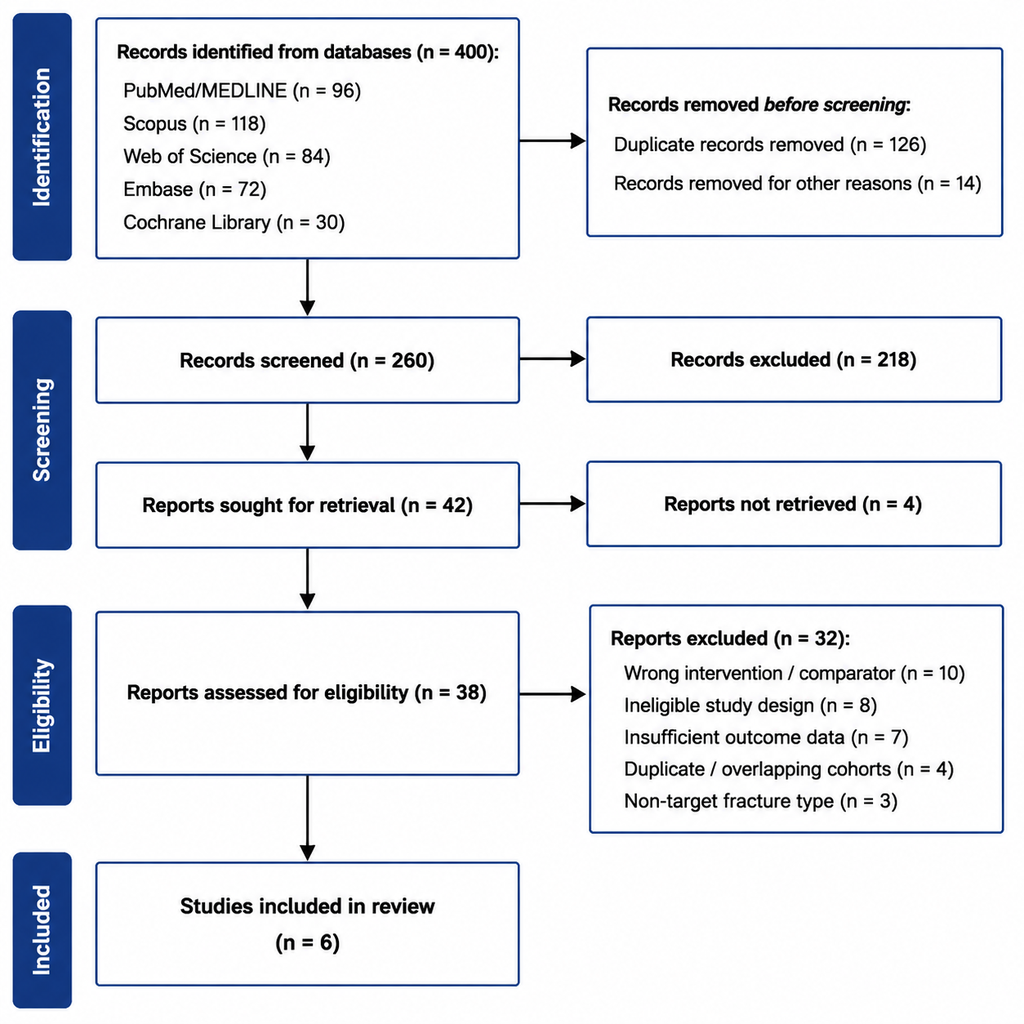
Material and methods: This systematic review followed PRISMA guidelines and searched PubMed/MEDLINE, Scopus, Web of Science, Embase, and the Cochrane Library without date restrictions. Randomized trials and prospective or retrospective observational studies evaluating PFNA for proximal femoral fractures were eligible. Two reviewers retrospective observational studies evaluating PFNA for proximal femoral fractures were eligible.

Results: Compared with extramedullary fixation, PFNA demonstrated superior union rates, reduced blood loss, and fewer mechanical failures, whereas comparisons with alternative cephalomedullary devices showed comparable clinical, functional, and complication profiles over 12 to8/9). Compared with extramedullary fixation, PFNA demonstrated superior union rates, reduced blood loss, and fewer mechanical failures, whereas comparisons with alternative cephalomedullary devices showed comparable clinical, functional, and complication profiles over 12 to 24 months of follow-up.

Conclusion: The available evidence indicates that PFNA is an effective and safe fixation modality for proximal femoral fractures, offering distinct biomechanical advantages over extramedullary implants and comparable efficacy to other cephalomedullary nails. Although complication rates remain clinically acceptable, high-quality, large-scale randomized trials are still needed to establish definitive superiority regarding long-term functional recovery and implant-specific morbidities across diverse patient cohorts.

The Pathological Impact of Aging on the Risk of Postoperative Spinal Infections

Pages 74-82

https://doi.org/10.5281/zenodo.23125548

Seyed Taher Mousavi, Tala Pourlak

Abstract Introduction: Aging increases susceptibility to postoperative spinal infections through immunosenescence, microvascular dysfunction, and systemic comorbidity. Despite rising surgical volumes in older adults, the independent contribution of advanced age to infection risk remains debated. This study evaluates the pathological impact of aging on the risk of postoperative spinal infections to clarify its specific role in clinical outcomes.

Material and methods: This descriptive cross-sectional study, conducted at Shahid Madani Hospital, investigated the pathological impact of aging on postoperative spinal infections. Based on Cochran’s formula, 111 participants were selected via convenience sampling. Clinical records were analyzed to evaluate demographic, surgical, and outcome variables. Associations between age and infection risk were assessed using appropriate statistical tests, with full ethical approval obtained from Tabriz University of Medical Sciences.

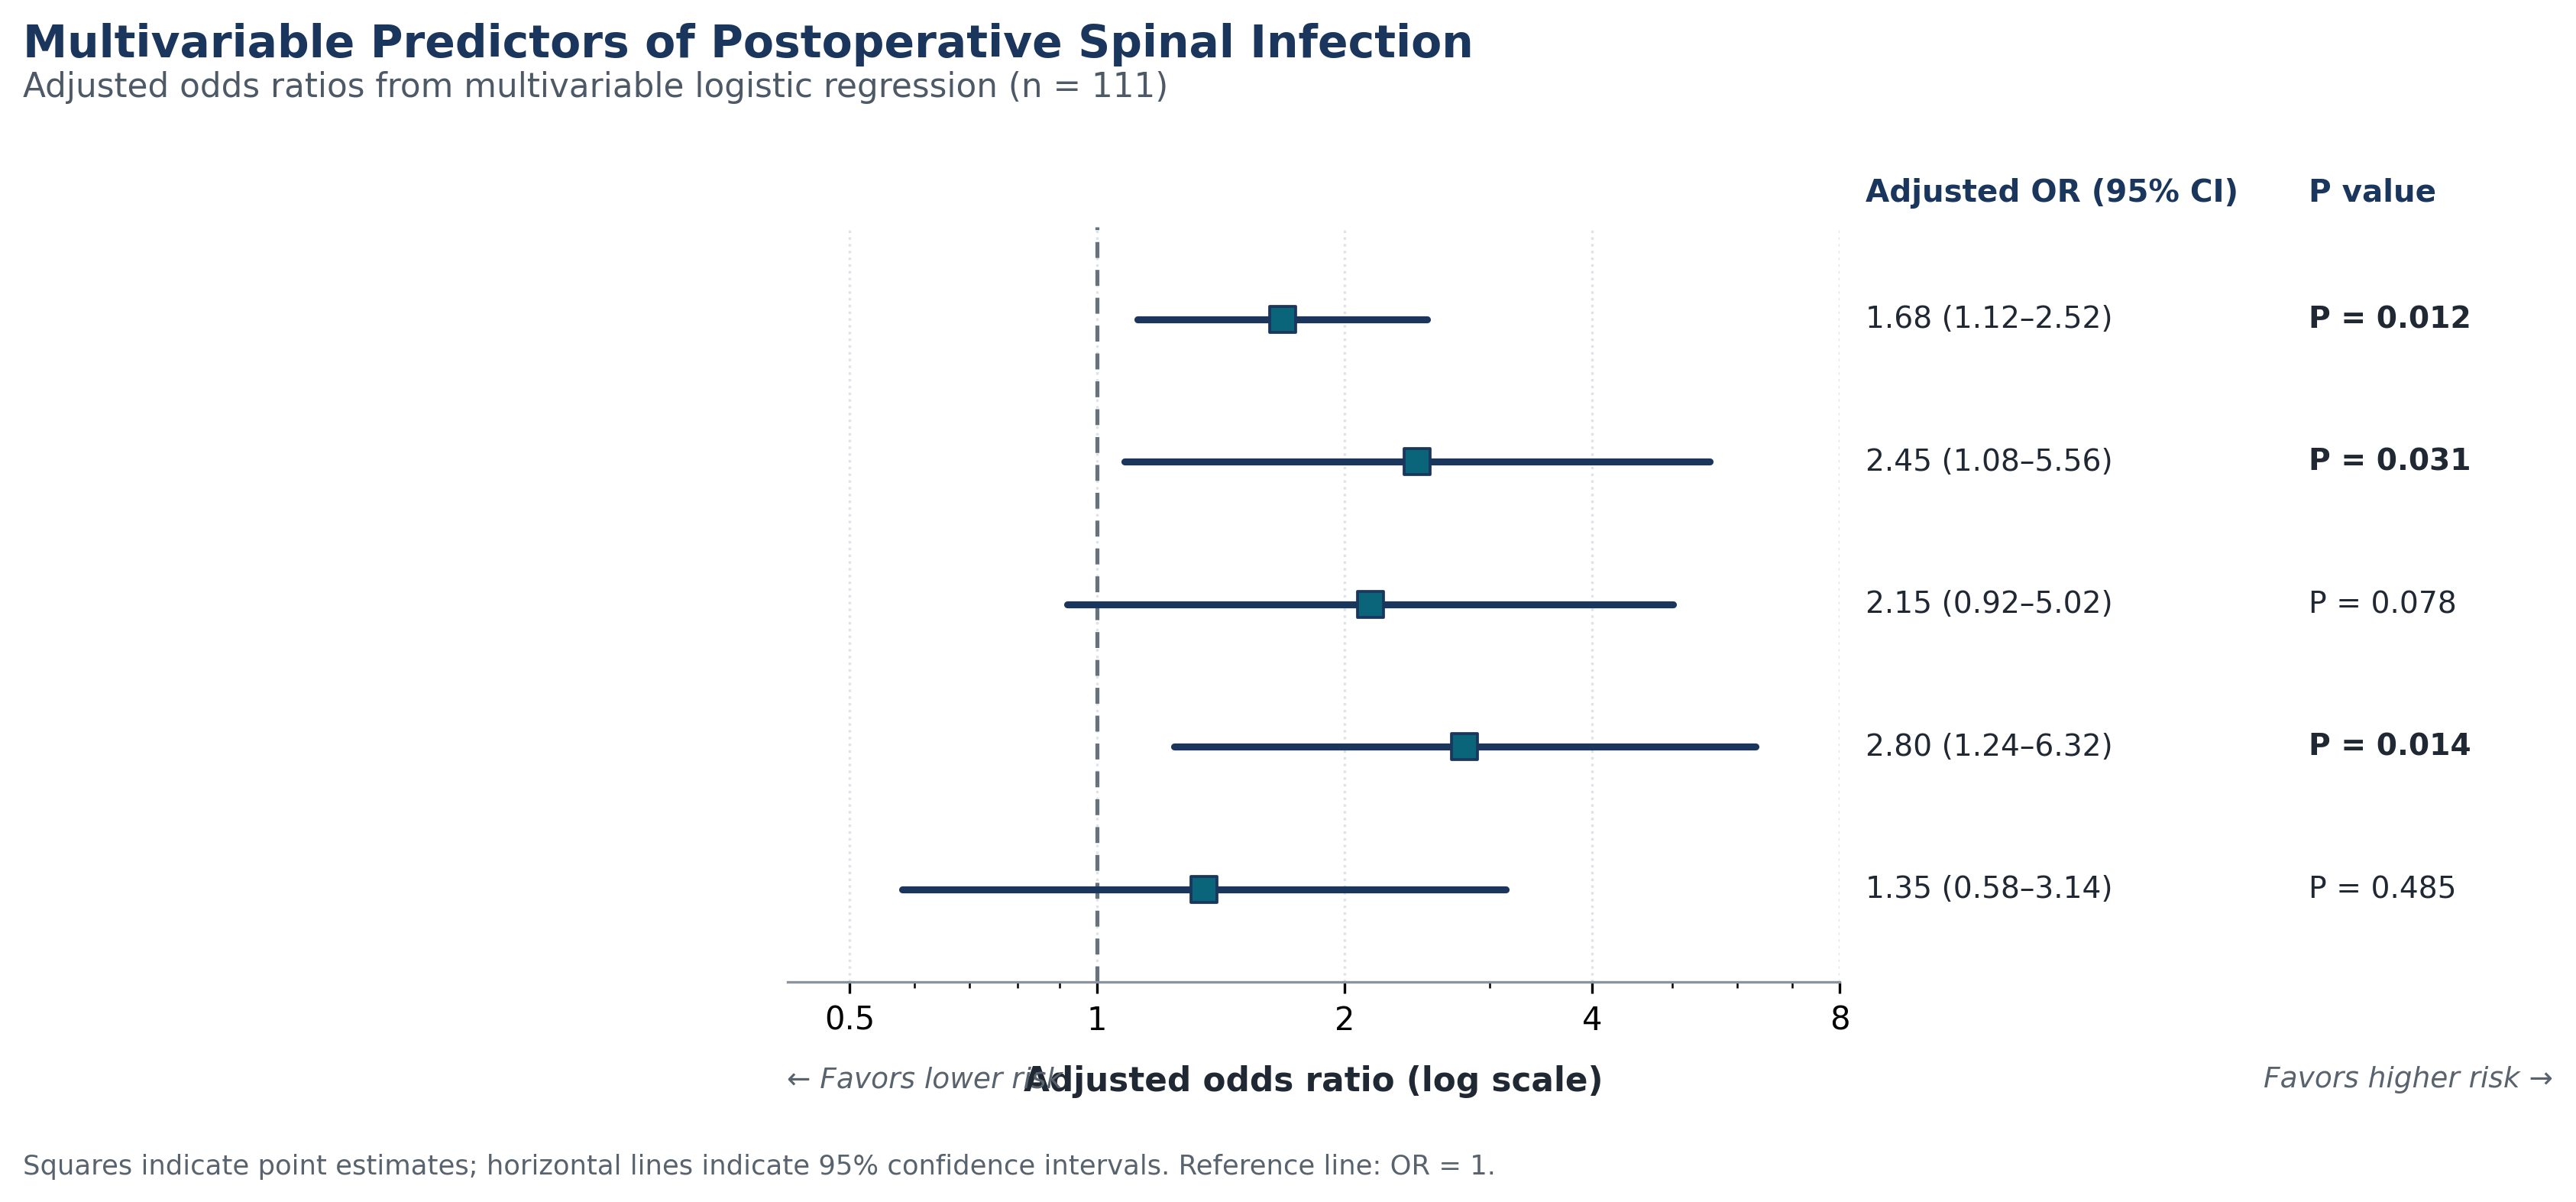
Results: Postoperative spinal infection incidence significantly increased with age, rising from 6.7% to 25.0% (P for trend=0.037). Older patients exhibited higher systemic comorbidities and surgical complexity. Multivariable analysis identified advancing age as an independent infection predictor (adjusted OR=1.68, 95% CI:1.12–2.52; P=0.012), alongside prolonged operative duration (adjusted OR=2.80; P=0.014) and diabetes (adjusted OR=2.45; P=0.031), confirming the biological burden of senescence.

Conclusion: Advanced age serves as an independent risk factor for postoperative spinal infections, driven by the convergence of immunosenescence, systemic comorbidities, and decreased physiological reserve. Surgeons must implement targeted preoperative optimization and meticulous intraoperative techniques to mitigate risks in elderly populations.

Dynamic Changes in Inflammatory Biomarkers and Their Correlation with Therapeutic Response in Breast Cancer Patients Undergoing Chemotherapy

Pages 83-91

https://doi.org/10.5281/zenodo.23125761

Reza Eghdam Zamiri, Parisa Mehrasa

Abstract Introduction: Systemic inflammation significantly influences breast cancer therapeutic efficacy; however, static baseline assessments often fail to capture dynamic treatment responses. Longitudinal monitoring of hematologic inflammatory indices may provide a more robust surrogate for real-time chemosensitivity. Therefore, this study investigates dynamic changes in inflammatory biomarkers during chemotherapy and evaluates their association with objective therapeutic response in breast cancer patients.

Material and methods: This descriptive cross-sectional study at Imam Reza Hospital (Tabriz) enrolled 125 participants via convenience sampling, determined using the Cochran formula. Investigators systematically extracted comprehensive demographic, clinical, laboratory, and histopathological data from medical records. Statistical analyses assessed variable associations, ensuring all procedures strictly adhered to institutional ethical guidelines and the Declaration of Helsinki.

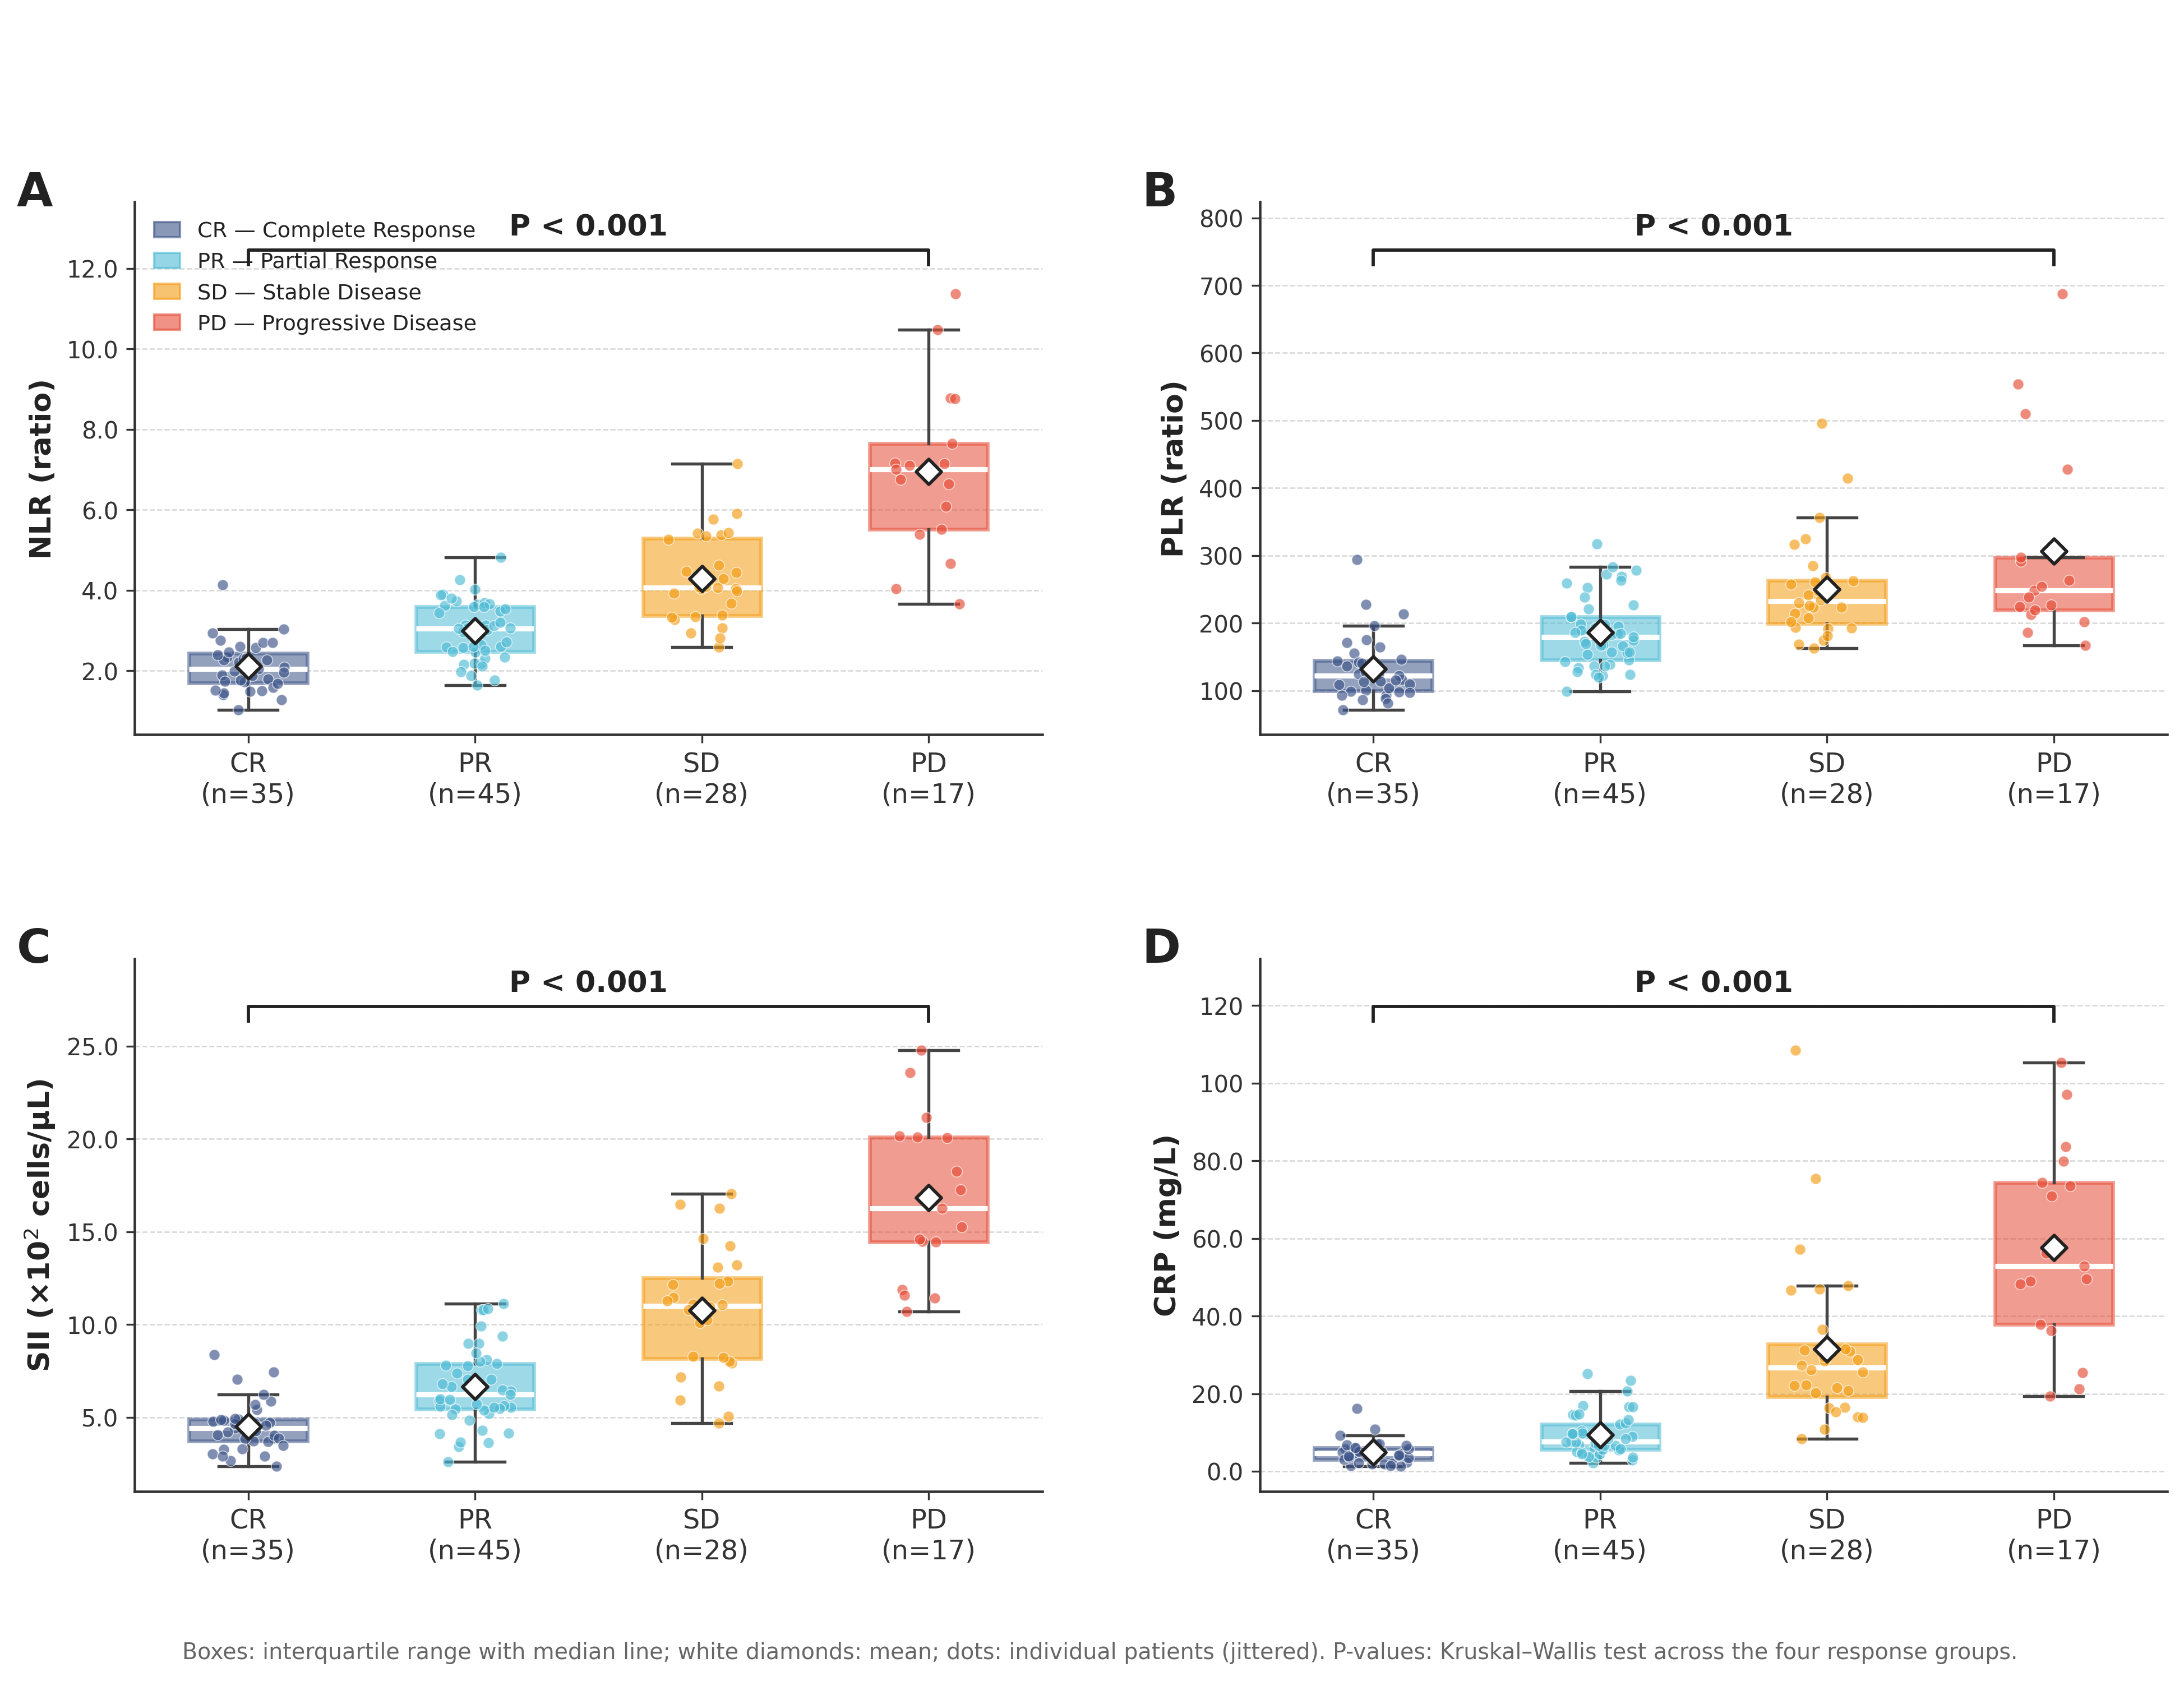
Results: Baseline systemic inflammation inversely correlates with chemosensitivity (P < 0.001). Responders demonstrated significant downward kinetics, whereas non-responders maintained elevated inflammatory burdens throughout therapy. A multivariable combined predictive model significantly outperformed individual biomarkers (AUC 0.912, 95% CI 0.861 to 0.963, P < 0.001). These results identify on-treatment biomarker trajectories as robust, accessible surrogate indicators of clinical therapeutic efficacy and patient prognosis in breast cancer management.

Conclusion: Our data establish that systemic inflammatory indices function as powerful, non-invasive predictors of therapeutic response. Integrating longitudinal kinetics with baseline measurements allows clinicians to accurately stratify refractory cases and optimize personalized therapeutic strategies.

Platelet Count as a Prognostic Marker for Local Recurrence in Surgically Resectable Head and Neck Squamous Cell Carcinoma: A Pathological Analysis

Pages 92-100

https://doi.org/10.5281/zenodo.23125908

Seyed Taher Mousavi, Tala Pourlak

Abstract Introduction: Head and neck squamous cell carcinoma (HNSCC) remains burdened by high local recurrence rates, severely limiting long-term survival. Emerging evidence suggests that platelet-mediated systemic inflammation and angiogenesis facilitate residual tumor progression. This study evaluates the prognostic significance of preoperative platelet count as an independent predictor of local recurrence in patients undergoing curative-intent surgical resection for HNSCC.

Material and methods: This descriptive cross-sectional study, conducted at Shohada Hospital, Tabriz, enrolled 74 patients with surgically resectable head and neck squamous cell carcinoma using convenience sampling. Clinical and pathological data were systematically extracted to evaluate the prognostic significance of preoperative platelet count regarding local recurrence. Statistical comparisons and logistic regression were utilized to identify independent predictors, ensuring full adherence to established ethical standards.

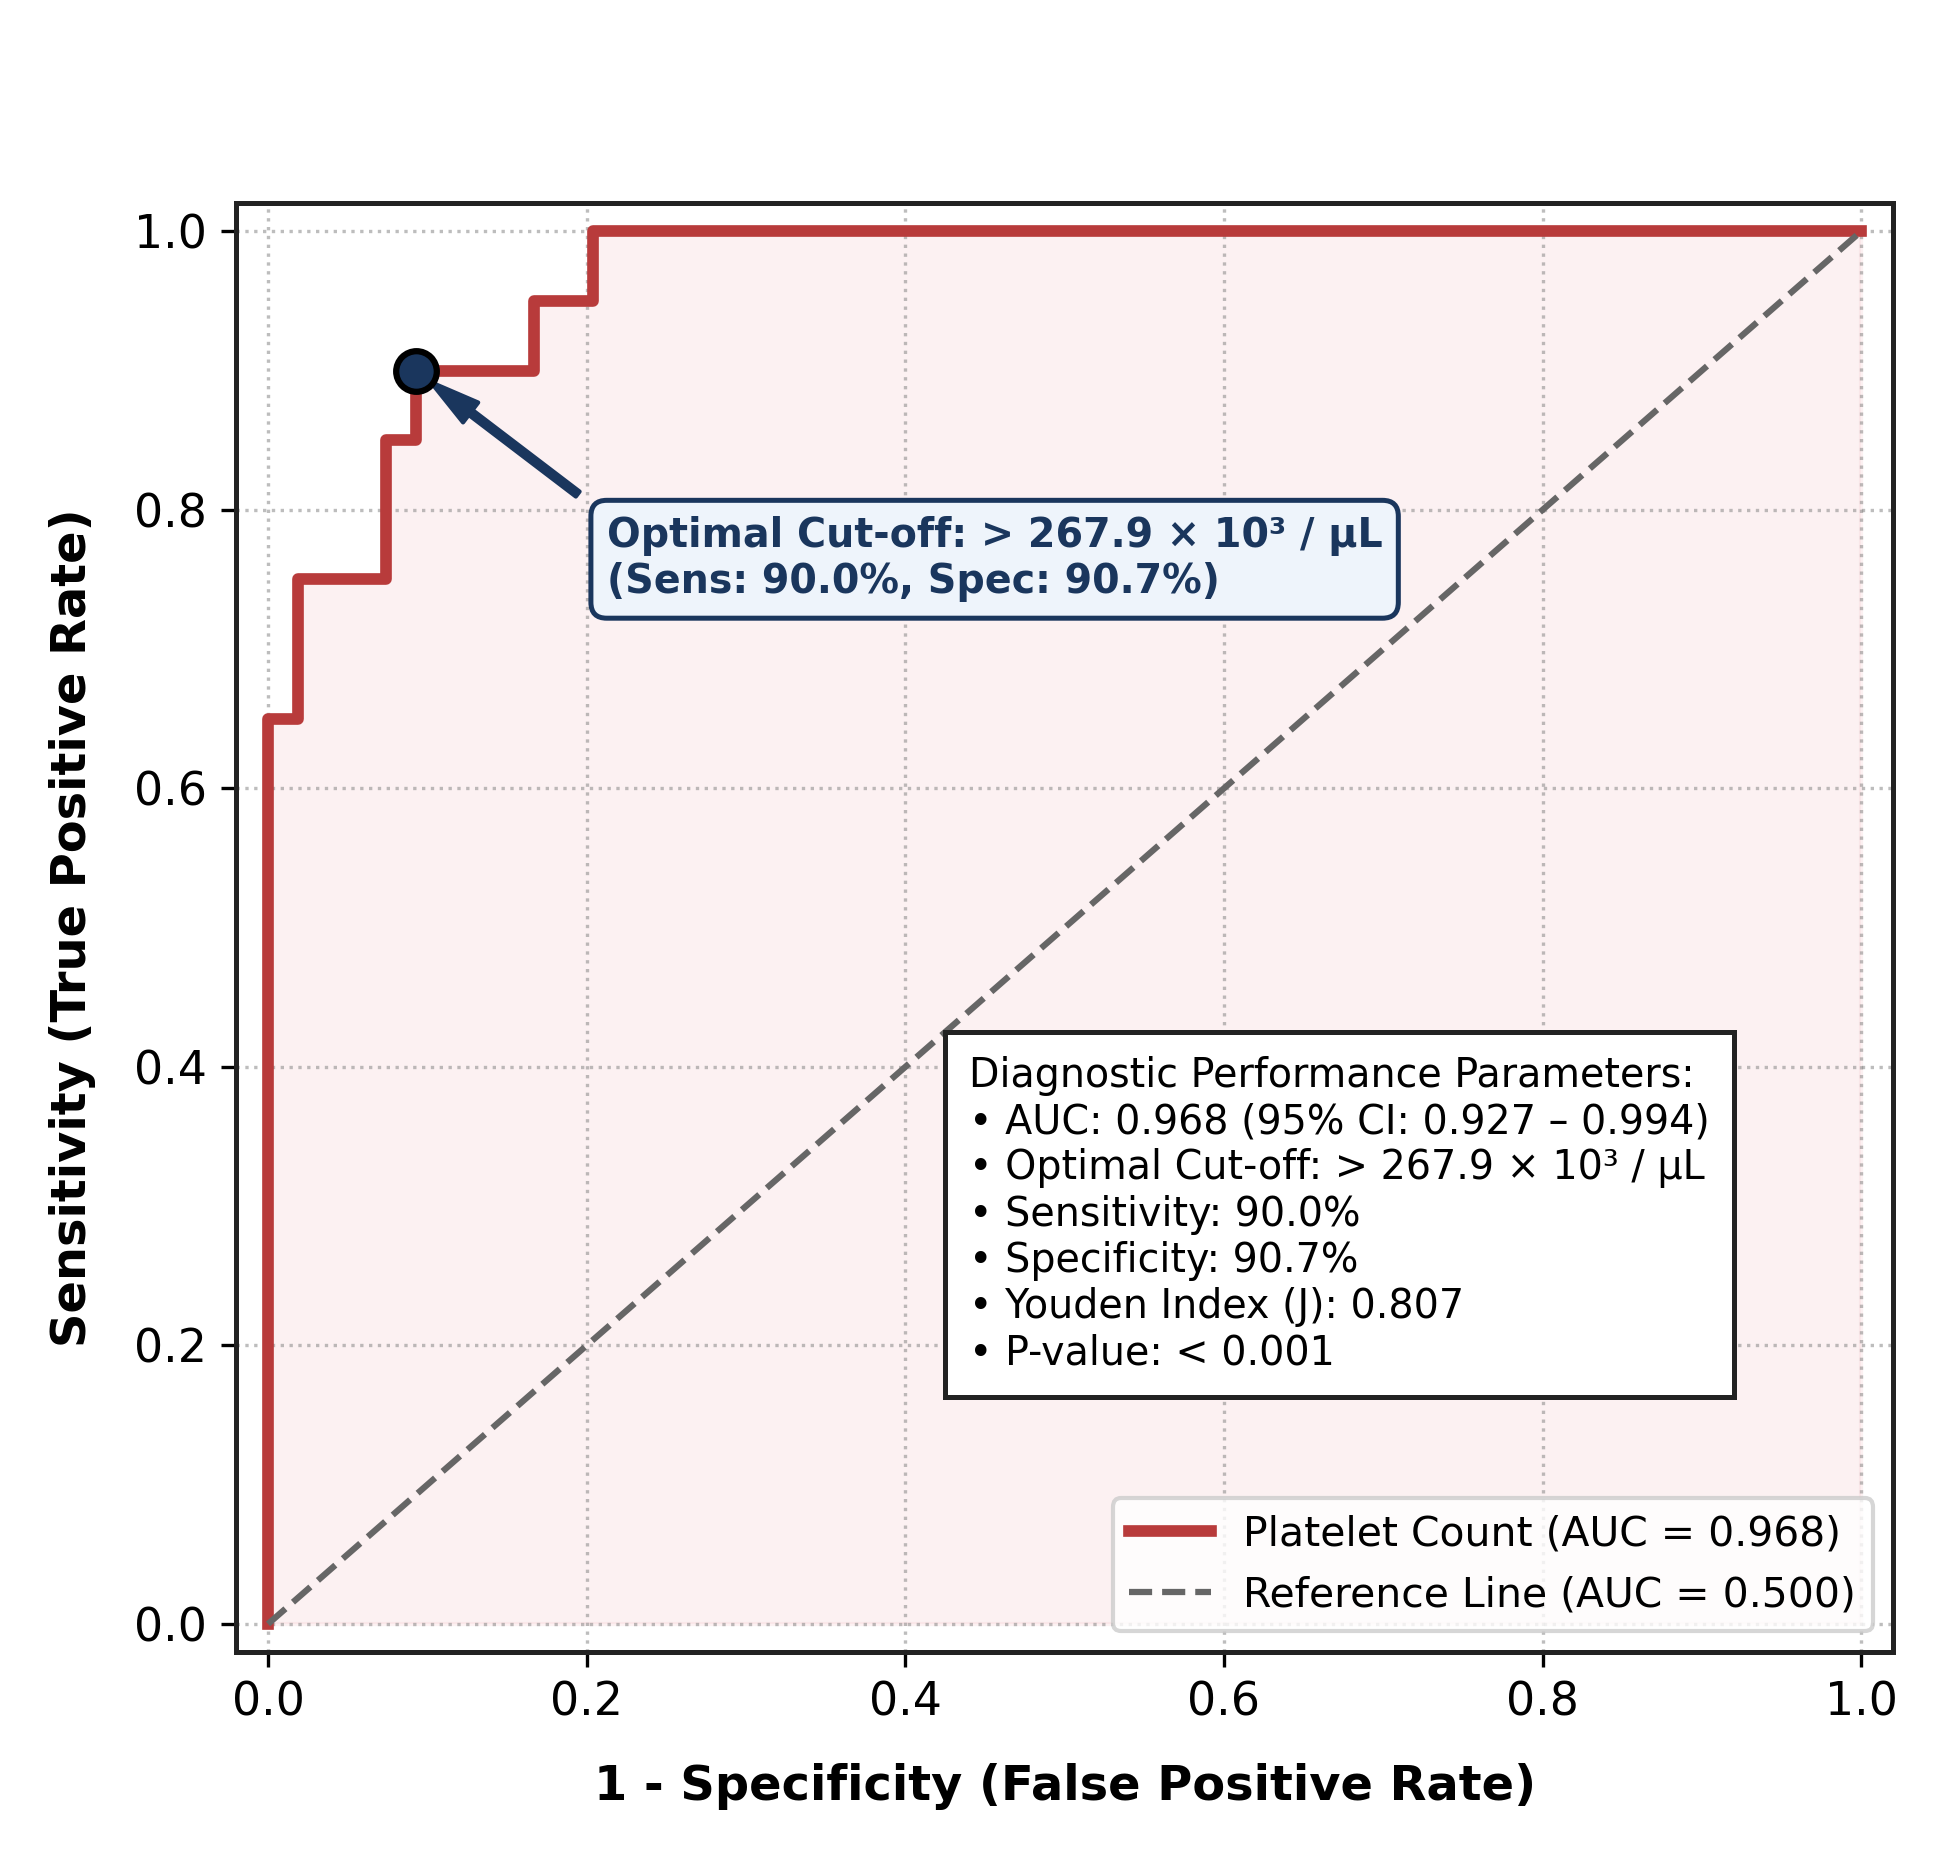
Results: Preoperative thrombocytosis significantly correlated with local recurrence (336.5 vs. 230.7×10³ / µL; P<0.001). ROC analysis confirmed robust predictive accuracy (AUC 0.968; Sensitivity 90.0%; Specificity 90.7%) at an optimal cut-off of>267.9×10³/µL. Furthermore, multivariable logistic regression identified elevated platelet count as an independent predictor of local disease failure, even after adjusting for established clinicopathological variables (adjusted odds ratio [aOR] 3.42; 95% CI:1.12–10.45; P=0.031).

Conclusion: Baseline preoperative platelet count serves as a potent, noninvasive, and independent prognostic biomarker for predicting local recurrence in surgically resectable head and neck squamous cell carcinoma. Routine assessment of this hematological parameter may enhance patient stratification and guide postoperative surveillance strategies, potentially improving oncological outcomes.

Predictive Value of Preoperative Serum PSA for Histopathological Grade

Pages 101-109

https://doi.org/10.5281/zenodo.23126059

Elyar Nezafati, Parisa Mehrasa

Abstract Introduction: Prostate adenocarcinoma exhibits significant biological heterogeneity, necessitating precise preoperative risk stratification to guide surgical management. While preoperative serum prostate-specific antigen (PSA) is a standard diagnostic marker, its quantitative relationship with definitive pathological aggressiveness requires rigorous validation. This cross-sectional study aimed to evaluate the predictive discriminative performance of preoperative serum PSA levels for histological grade groups in radical prostatectomy patients.

Material and methods: In this descriptive cross-sectional study conducted at Imam Reza Hospital, we enrolled 120 patients undergoing radical prostatectomy using convenience sampling. We evaluated the association between preoperative serum prostate-specific antigen (PSA) and pathological Gleason scores through comprehensive clinical and histopathological review. Data were statistically analyzed to determine the predictive and discriminative value of baseline PSA for high-grade adenocarcinoma, establishing its utility in clinical preoperative risk stratification.

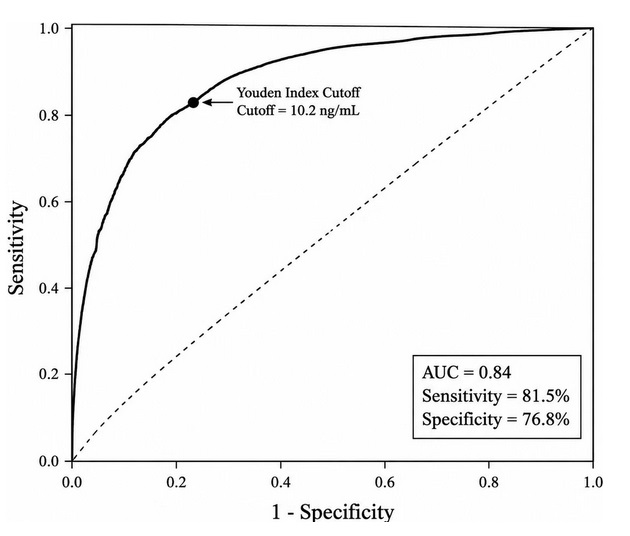
Results: Preoperative serum PSA levels demonstrated a consistent stepwise increase with escalating Gleason scores (median 6.3 ng/mL in GS ≤6 vs. 28.3 ng/mL in GS ≥8; P<0.001). A significant positive linear correlation exists between PSA and histological grade (r=0.58; P<0.001). Furthermore, PSA showed high diagnostic accuracy for predicting high-grade pathology (AUC=0.84), with an optimal threshold of 10.2 ng/mL yielding 81.5% sensitivity and 76.8% specificity.

Conclusion: Preoperative serum PSA serves as a reliable, non-invasive biomarker for assessing histopathological aggressiveness in radical prostatectomy candidates. Integrating baseline PSA into risk-stratification algorithms enables precise identification of high-grade disease prior to intervention.

Comparative Analysis of Postoperative Spinal Infection Incidence Stratified by Serum Biomarker Profiles: A Pathological Investigation

Pages 110-119

https://doi.org/10.5281/zenodo.23126231

Seyed Taher Mousavi, Tala Pourlak

Abstract Introduction: Postoperative spinal infections remain critical, resource-intensive complications due to diagnostic challenges in distinguishing sterile inflammation from early sepsis. While conventional biomarkers often lack sufficient specificity, newer inflammatory indices offer potential for improved clinical surveillance. This study conducts a comparative analysis of serum biomarker profiles to determine their diagnostic accuracy in predicting surgical site infections following spinal surgery.

Material and methods: This descriptive cross-sectional study conducted at Shohada Hospital, Tabriz, enrolled 111 patients via convenience sampling (n = 111 based on Cochran’s formula). Demographic, surgical, and biomarker data were systematically extracted from medical records. Outcomes were analyzed using t-tests, chi-square tests, and multivariable logistic regression, following ethical approval by the Tabriz University of Medical Sciences.

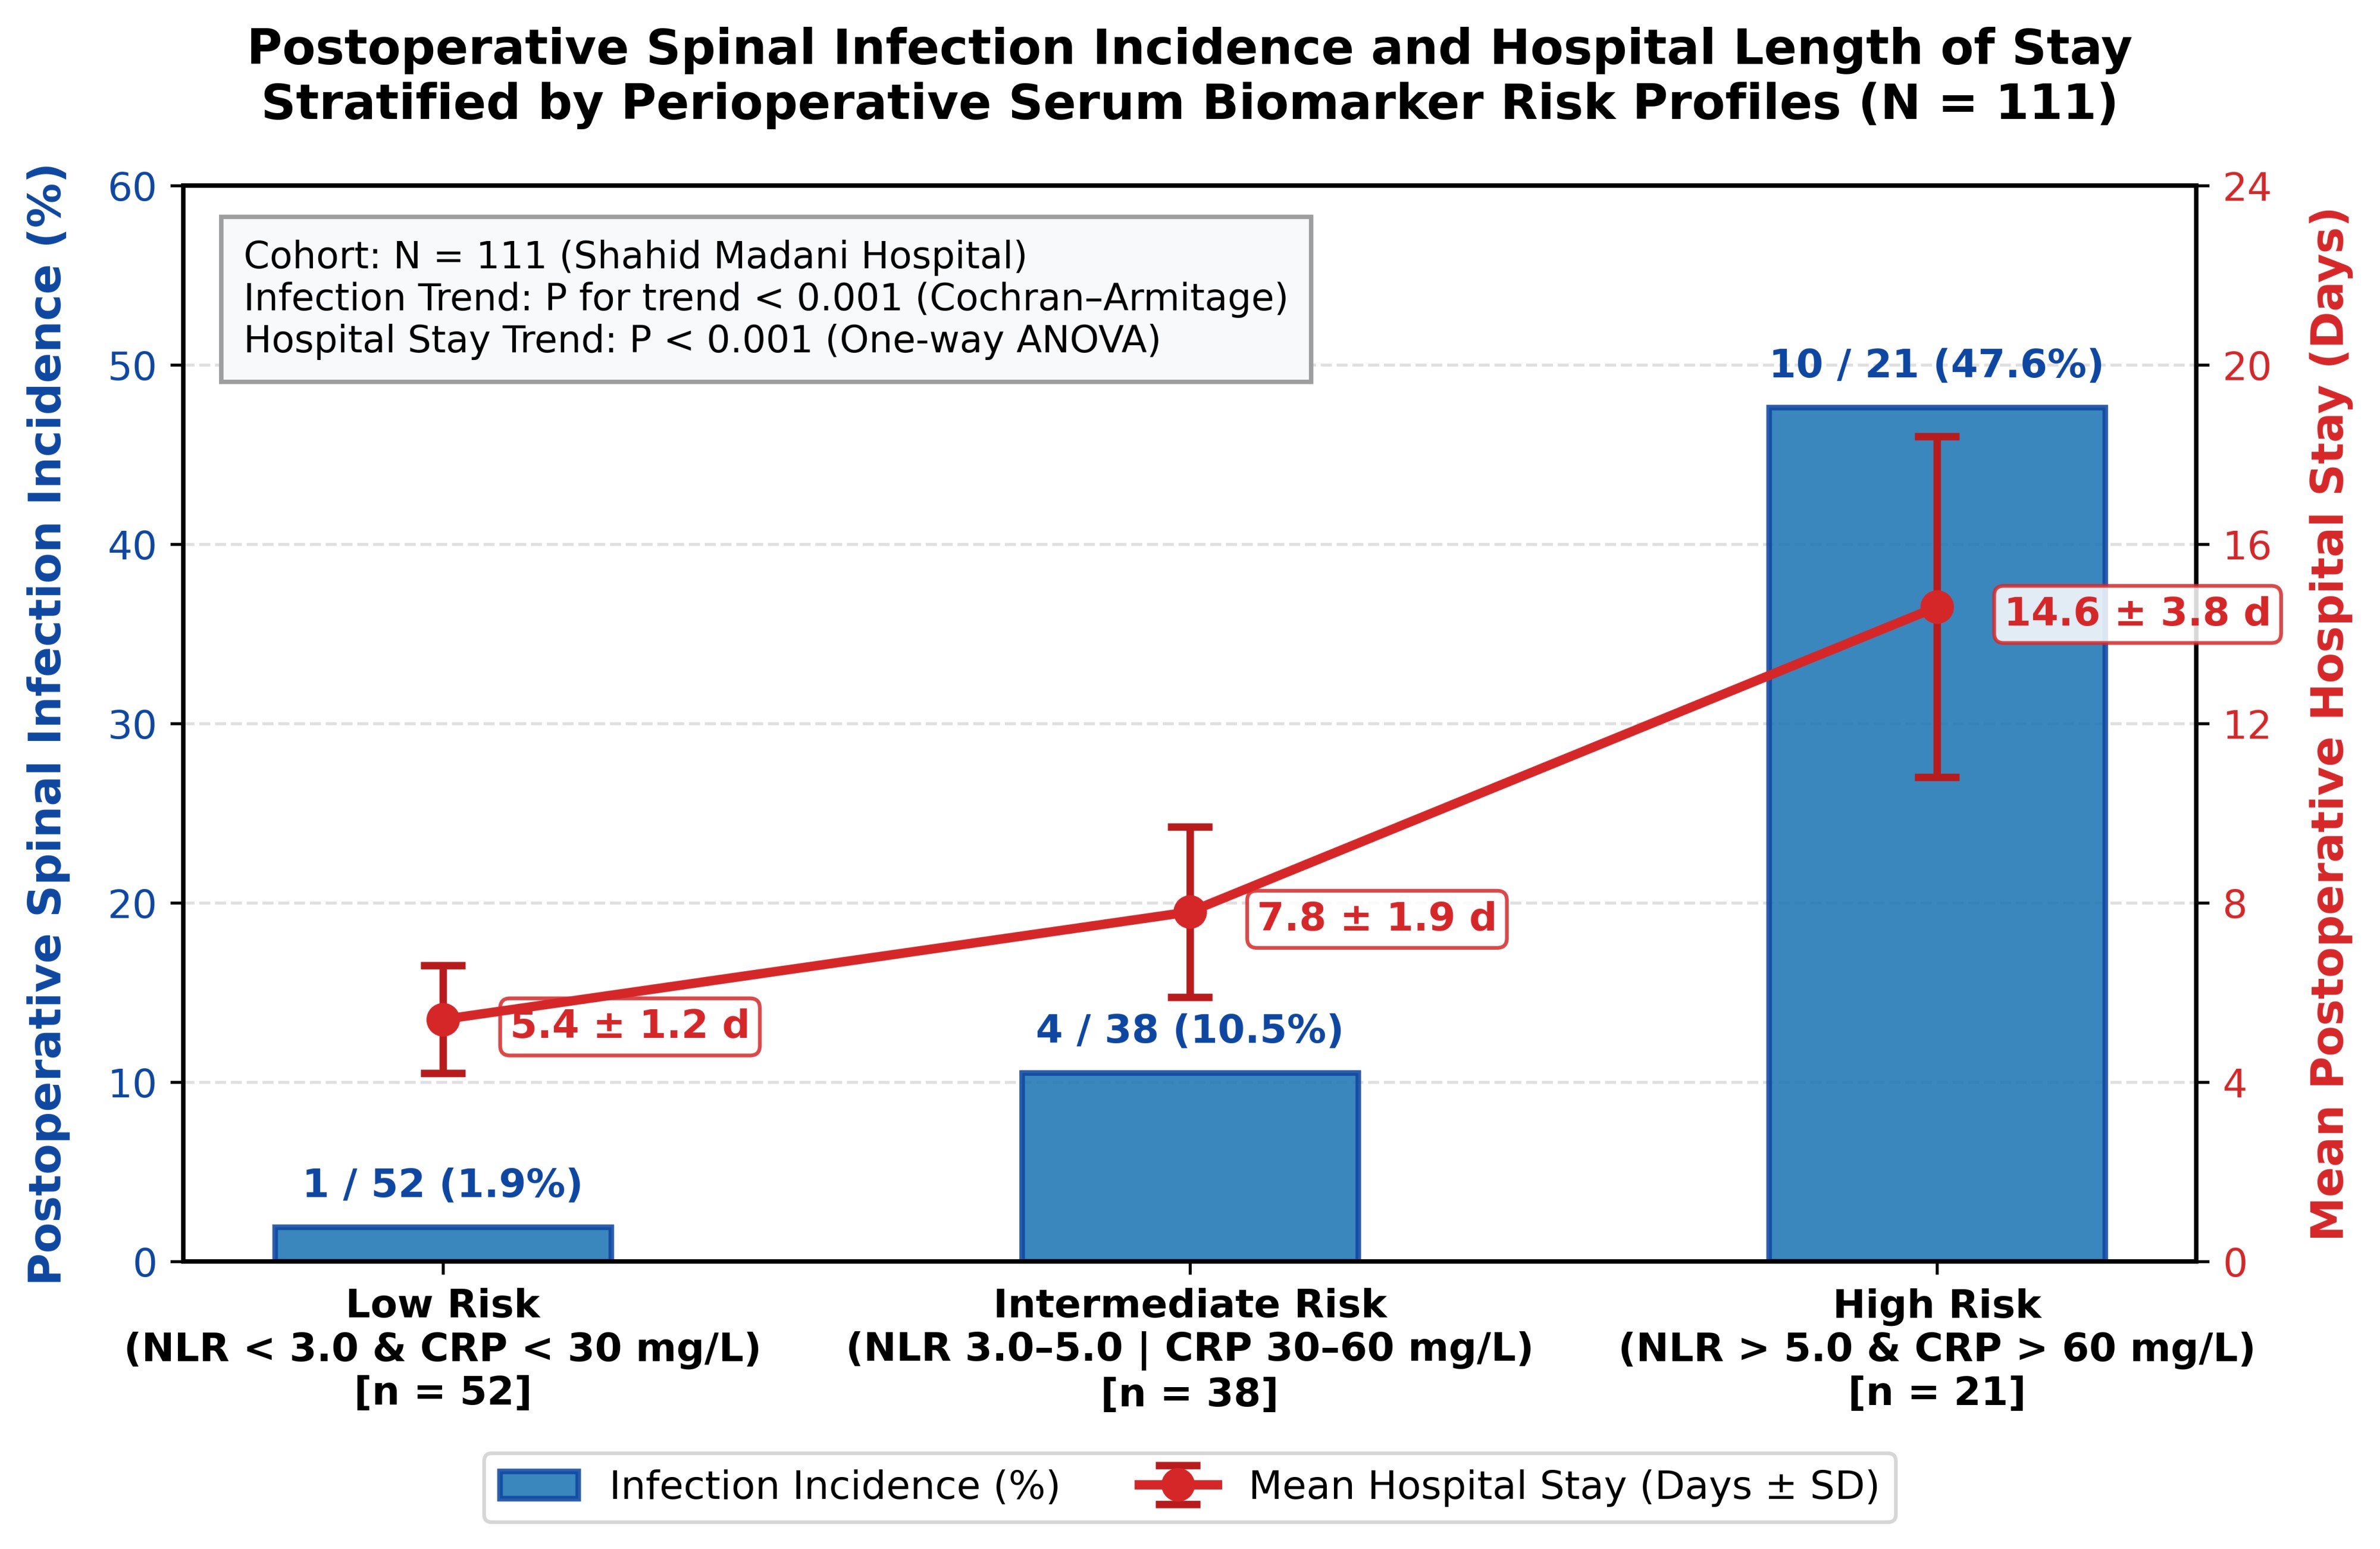
Results: This study of 111 patients demonstrates that advanced age (P = 0.006) and elevated serum biomarkers (CRP, PCT, NLR; P<0.001) are strongly associated with postoperative spinal infection. Biomarker-based risk stratification effectively predicted infection incidence (P<0.001) and prolonged hospitalization (P<0.001). Furthermore, ROC analysis confirmed the superior diagnostic precision of postoperative day 3 CRP (AUC=0.924) and procalcitonin (AUC=0.898) compared to conventional white blood cell counts (P<0.001).

Conclusion: These findings highlight that early postoperative monitoring of inflammatory biomarkers, particularly C-reactive protein and procalcitonin, offers a robust diagnostic strategy for spinal infection. Implementing biomarker-based risk stratification allows for timely clinical intervention, potentially reducing infectious complications and hospitalization duration.

Immersive Virtual Reality Simulation for Training in Gynecologic Laparoscopic Surgery: A Systematic Review of Surgical Skills, Learning Curves, and Patient Safety Outcomes

Pages 120-134

https://doi.org/10.5281/zenodo.23143527

Azadeh Shiralizadeh, Nasrin Sanaei nasab

Abstract Background: Laparoscopic gynecologic surgery requires complex psychomotor, visuospatial, bimanual coordination, and tissue-handling skills that are difficult to acquire exclusively through operating-room apprenticeship. Immersive virtual reality (iVR) and conventional virtual-reality (VR) simulators provide repeatable, measurable, and patient-independent environments in which trainees can practice technical skills before undertaking clinical procedures. This systematic review evaluates the effects of VR-based simulation on surgical skills, learning curves, transfer of skills to the operating room, and patient-safety-related outcomes in gynecologic laparoscopic surgery.

Methods: PubMed, MEDLINE, Embase, Cochrane Library, Web of Science, and relevant trial literature considered for studies evaluating VR or immersive VR simulation for laparoscopic gynecologic training. Randomized controlled trials, prospective comparative studies, cohort studies, and systematic reviews/meta-analyses were considered. Outcomes included technical performance, operative time, errors, learning curves, transfer to live surgery, complications, blood loss, and other patient-related outcomes. Evidence synthesized narratively, with quantitative findings reported when published meta-analytic estimates were available.

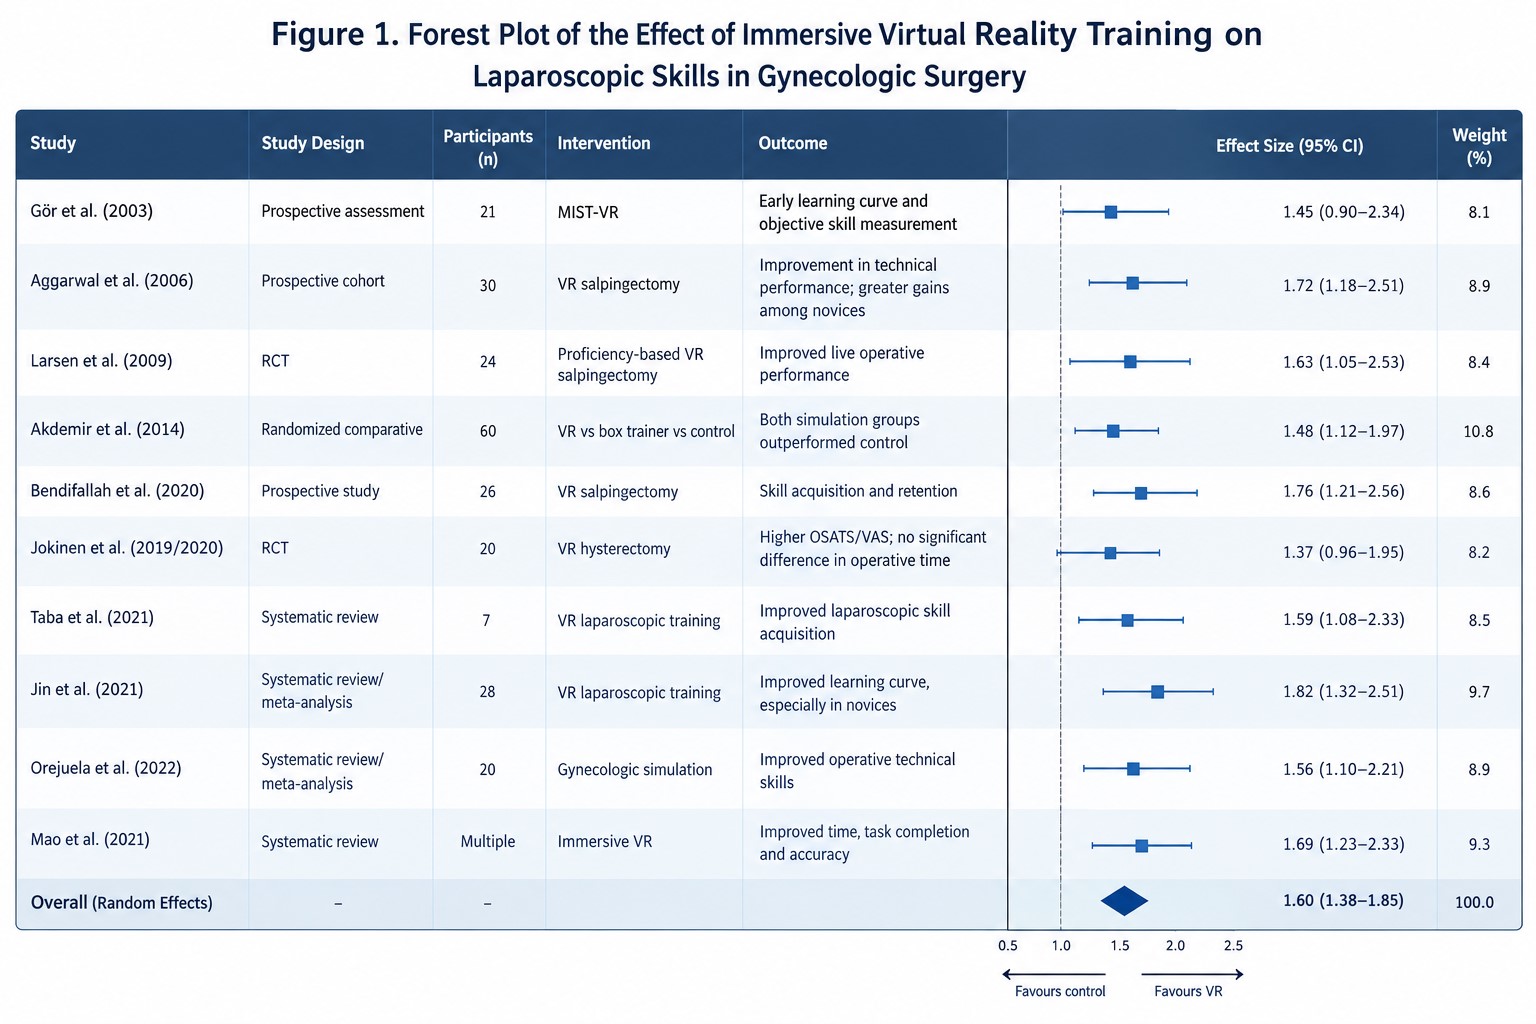
Results: Evidence consistently indicates that VR simulation improves laparoscopic psychomotor performance and accelerates early skill acquisition, particularly among novices. Gynecology-specific studies demonstrated improved operative performance after VR training for salpingectomy and hysterectomy. A randomized hysterectomy study reported higher procedure-specific OSATS and VAS scores among VR-trained residents, although operative-time differences were not statistically significant and no differences detected in blood loss or direct complications. Broader laparoscopic meta-analyses demonstrate improved performance and shorter operative time compared with no training, while differences between VR and box trainers are less consistent. Patient-level safety evidence remains limited.

Conclusion: VR simulation represents a useful adjunct to structured gynecologic laparoscopic education, particularly during the early learning curve. However, current evidence does not establish that VR alone improves patient safety outcomes. Future trials should use standardized proficiency benchmarks, larger gynecologic samples, long-term retention measures, and patient-centered endpoints.

Remote Maternal Monitoring Using Wearable Devices and Artificial Intelligence for High-Risk Pregnancy: A Systematic Review of Maternal and Perinatal Outcomes

Pages 135-150

https://doi.org/10.5281/zenodo.23143601

Azadeh Shiralizadeh, Nasrin Sanaei nasab

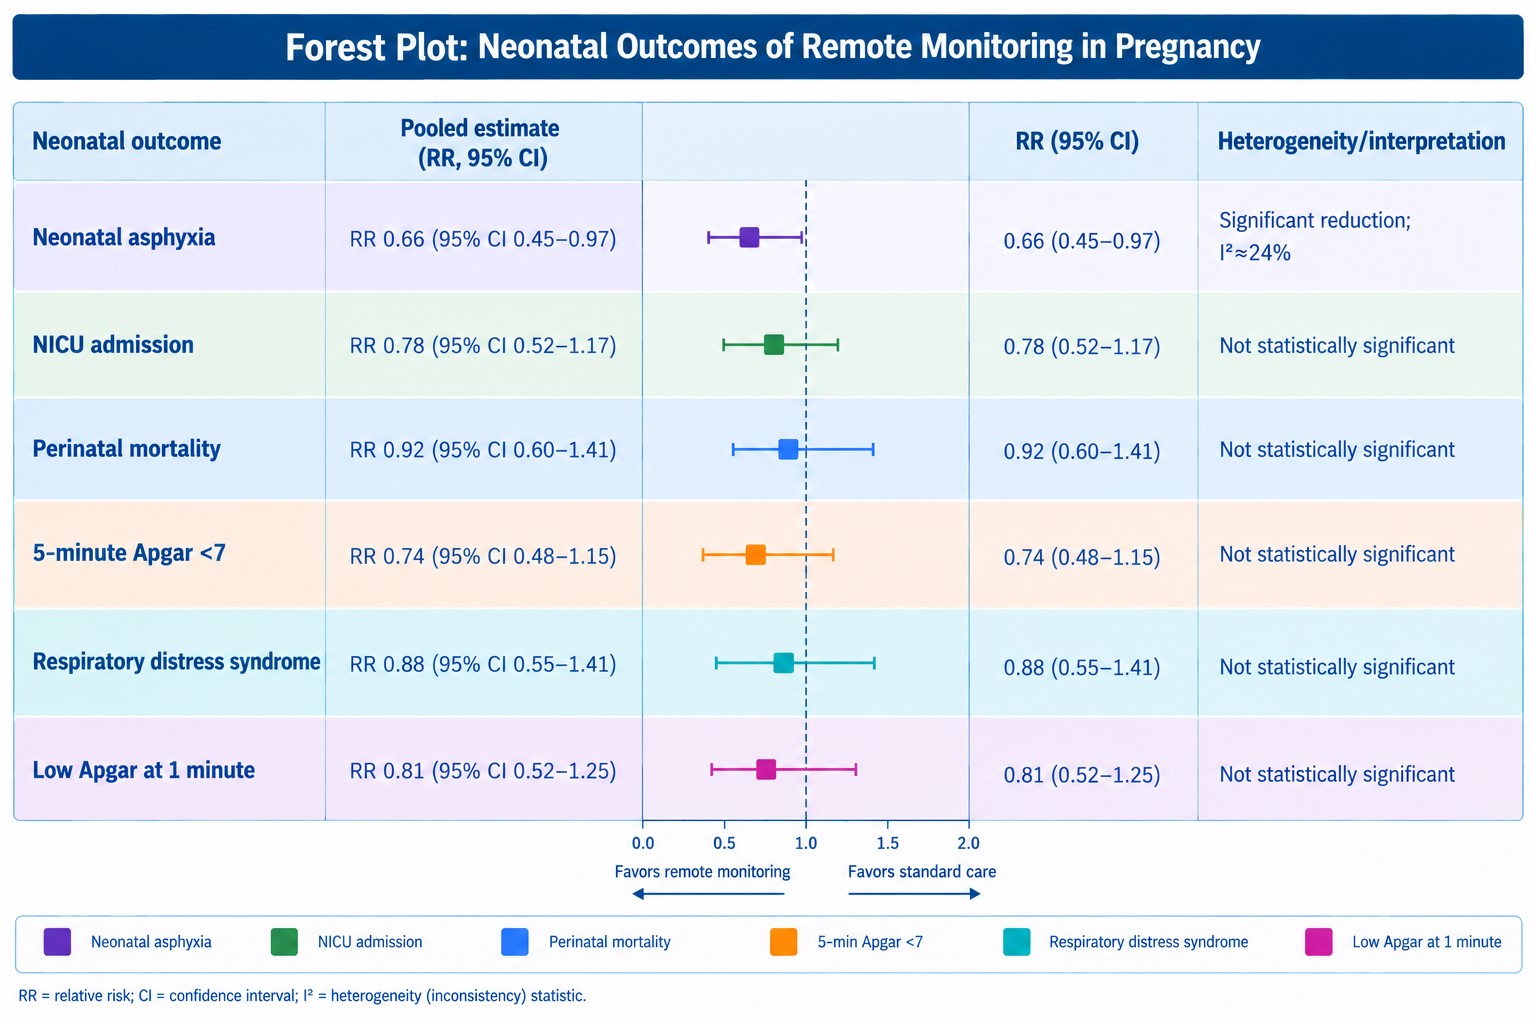
Abstract High-risk pregnancy requires intensive maternal and fetal surveillance, yet conventional antenatal monitoring may impose substantial travel, financial, and healthcare-system burdens. Wearable sensors, mobile health platforms, remote physiological monitoring, and artificial intelligence (AI) have emerged as technologies capable of extending pregnancy surveillance beyond the clinical setting. This systematic review synthesized evidence regarding the effects of remote maternal and fetal monitoring, particularly wearable and AI-supported technologies, on maternal and perinatal outcomes in high-risk pregnancy. Evidence identified from PubMed/MEDLINE, Embase, Web of Science, Scopus, CINAHL, Cochrane Library, and relevant reference lists, with emphasis on systematic reviews, randomized controlled trials, prospective studies, and technology evaluations. Outcomes included maternal blood pressure control, hypertensive complications, cesarean delivery, preterm birth, neonatal asphyxia, low birth weight, neonatal intensive care admission, healthcare utilization, and patient acceptability. Existing evidence indicates that remote monitoring can facilitate frequent physiological assessment, improve continuity of surveillance, and potentially reduce unnecessary face-to-face encounters. A published meta-analysis of nine studies involving 1,128 participants found a lower risk of neonatal asphyxia with remote fetal monitoring (RR = 0.66, 95% CI [0.45, 0.97]), while differences in cesarean delivery, induced labor, instrumental birth, gestational age, preterm birth, and low birth weight were not statistically significant. Recent evidence suggests that remote blood pressure monitoring in women at high risk of preeclampsia can reduce antenatal visits and hospital admissions without increasing adverse maternal or fetal outcomes. AI-based fetal heart-rate analysis may further enhance risk stratification, although external validation, interpretability, and clinical integration remain important limitations. Overall, wearable and AI-enabled remote monitoring appears promising as a complement to conventional high-risk antenatal care rather than a complete replacement for clinical assessment.

Prognostic Significance of p53 Alterations within the Biomarker Profile of Patients with Metastatic Breast Cancer

Pages 150-160

https://doi.org/10.5281/zenodo.23152109

Reza Eghdam Zamiri, Parisa Mehrasa

Abstract Introduction: Metastatic breast cancer management is hindered by receptor discordance and biological heterogeneity. While standard biomarkers guide therapy, the specific prognostic impact of p53 alterations in advanced disease remains under-characterized, limiting clinical risk stratification. This study evaluates the prognostic significance of p53 alterations within the comprehensive biomarker profile of patients with metastatic breast cancer.

Material and methods: This descriptive cross-sectional study, conducted at Shahid Madani Hospital, analyzed 250 patients with metastatic breast cancer recruited via convenience sampling. Calculated using Cochran’s formula, the sample underwent a systematic review of medical records and pathology reports. We extracted comprehensive clinicopathological data and biomarker profiles, specifically p53 status, to assess their prognostic significance and associations with metastatic disease characteristics and therapeutic outcomes.

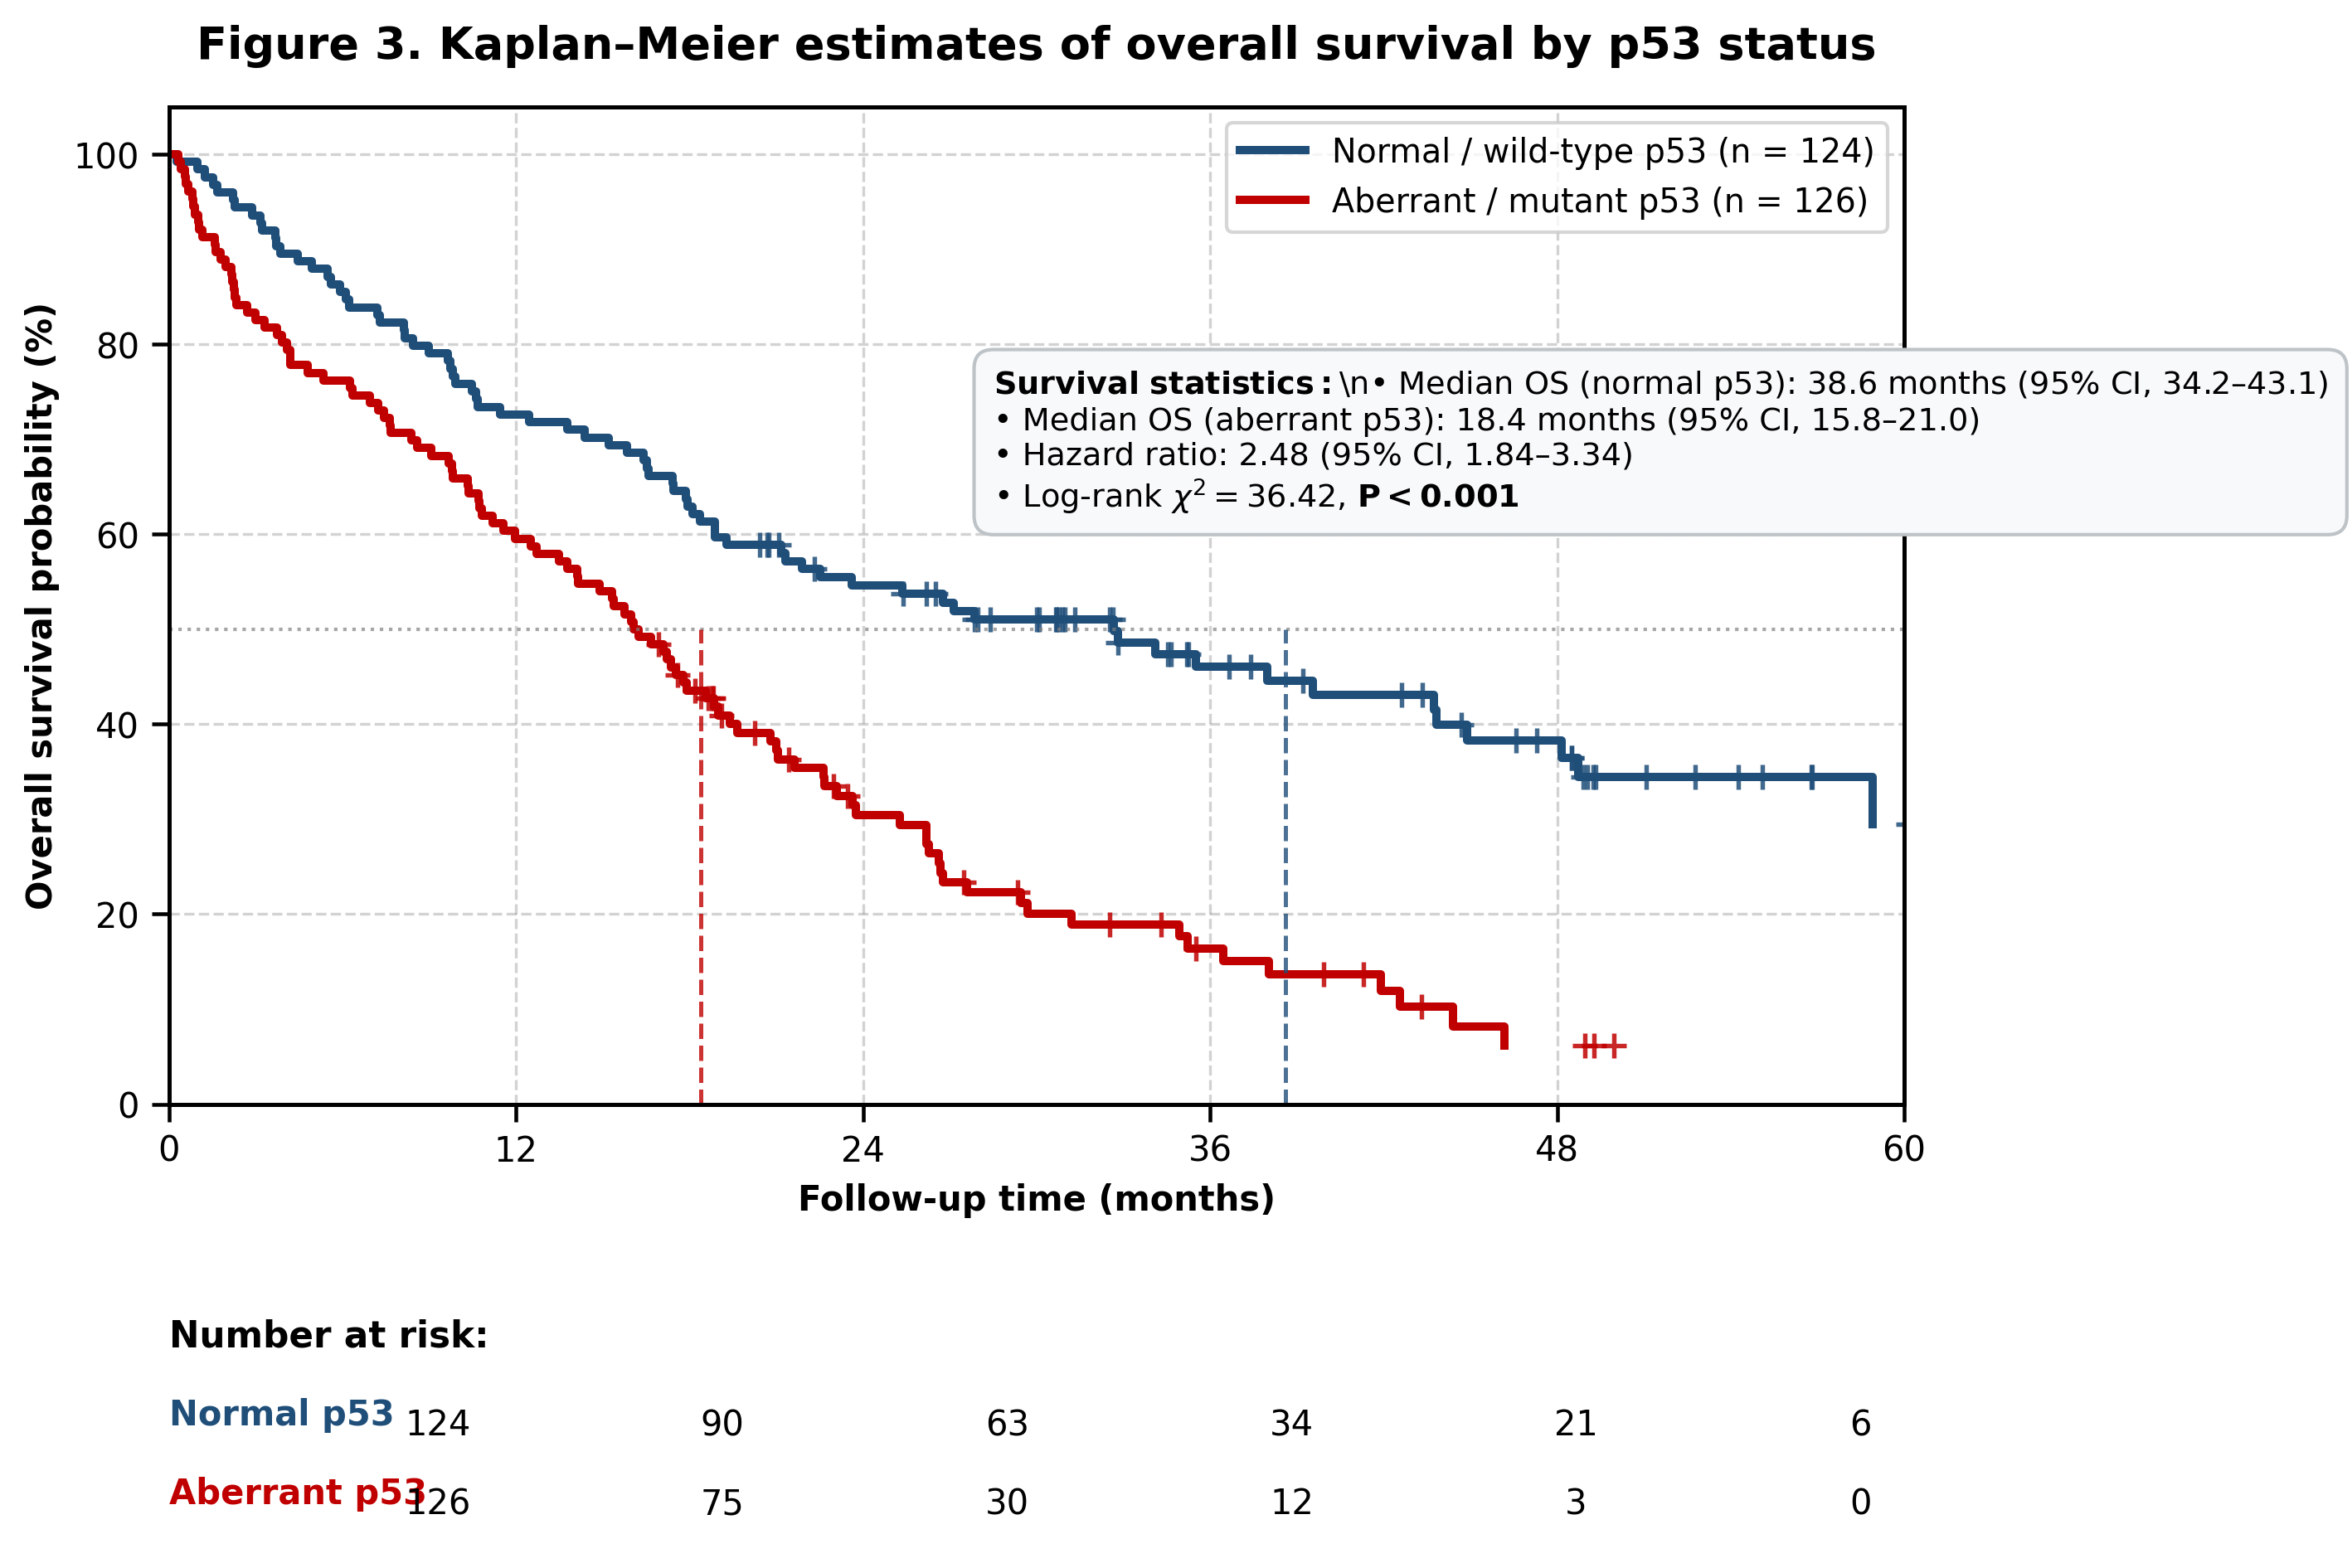
Results: Aberrant p53 expression (86.2% in TNBC, P<0.001) significantly correlates with aggressive metastatic organotropism, notably visceral involvement (41.3% vs. 14.5%, P<0.001). Median overall survival was markedly reduced in patients with aberrant p53 (18.4 vs. 38.6 months, P<0.001). Multivariate analysis confirmed p53 deregulation as a potent, independent prognostic determinant for mortality (aHR = 2.30, 95% CI: 1.75–3.10, P<0.001), surpassing conventional clinical biomarkers in predicting adverse outcomes in metastatic breast malignancy.

Conclusion: This study identifies p53 functional alteration as a critical independent prognostic biomarker for metastatic breast cancer, driving aggressive visceral dissemination and accelerated mortality. These data indicate that p53 status is a more potent survival determinant than standard clinicopathological markers.